Tag: IBS

  • SIBO: Symptoms, Causes, and Treatment Options

    SIBO: Symptoms, Causes, and Treatment Options

    SIBO: Symptoms, Causes, and Treatment Options

    Small intestinal bacterial overgrowth is one of the most underdiagnosed causes of chronic bloating, gas, and digestive discomfort in American adults.

    Introduction

    Meet David, 47, who spent two years being told his persistent bloating, stomach cramps, and unpredictable bowel habits were “just stress.” He tried elimination diets, probiotics, and antacids — but nothing brought lasting relief. It wasn’t until a gastroenterologist ordered a breath test that David finally got a diagnosis: small intestinal bacterial overgrowth, or SIBO.

    According to research published in the American Journal of Gastroenterology, SIBO may affect up to 80% of people diagnosed with irritable bowel syndrome — and a significant portion of them don’t yet know the real culprit behind their symptoms.

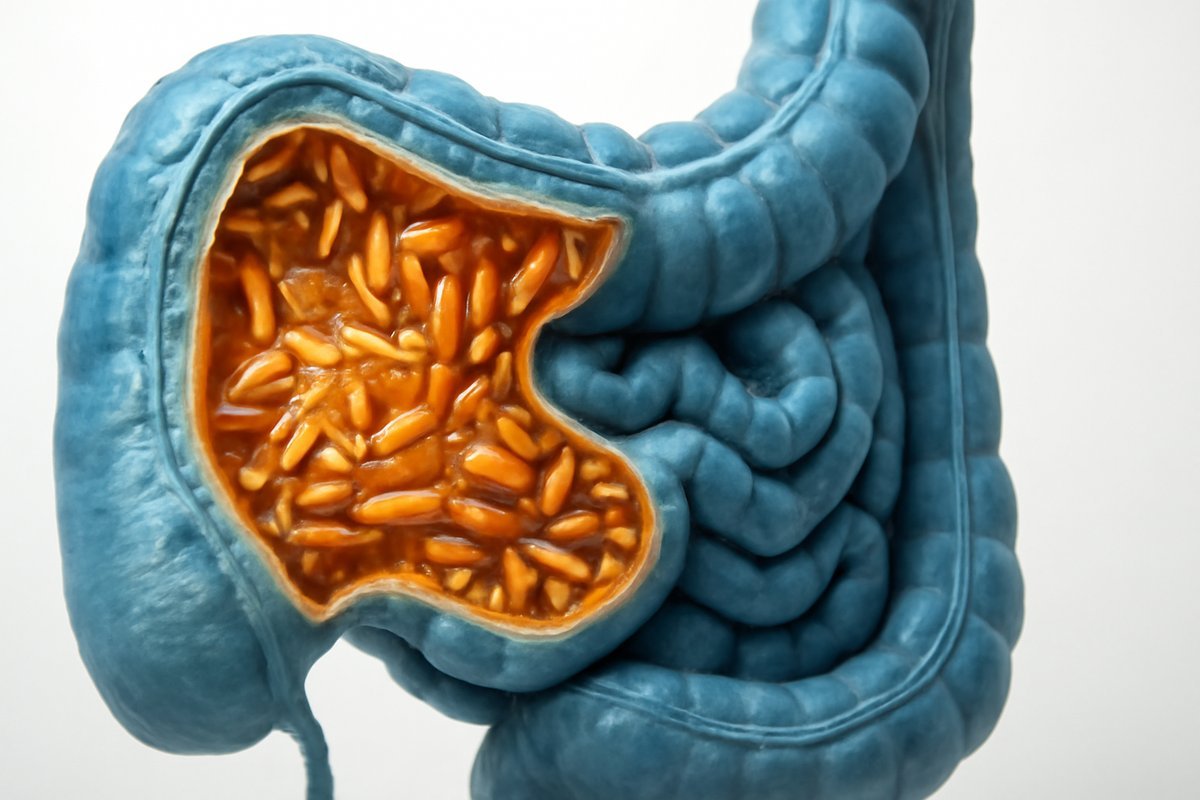
    SIBO occurs when bacteria that normally live in the large intestine migrate and multiply inside the small intestine, where they disrupt digestion and nutrient absorption. In this guide, you’ll learn what SIBO is, how to recognize its signs, what causes it, how it’s diagnosed, and what your treatment options look like — all in plain, practical terms you can bring to your next doctor’s visit.

    What Is SIBO?

    Small intestinal bacterial overgrowth (SIBO) is a condition in which an abnormally large number of bacteria colonize the small intestine — the part of your digestive tract responsible for absorbing most of your nutrients. Normally, the small intestine contains relatively few bacteria compared to the large intestine (colon). When that balance is disrupted, the overgrown bacteria ferment carbohydrates before proper digestion occurs, producing excess gas and triggering inflammation.

    SIBO is not a rare condition. Research from the NIH suggests it is present in 6 to 15 percent of healthy individuals and in up to 80 percent of people with IBS-like symptoms. Because its symptoms overlap with so many other digestive disorders, it often takes years to diagnose correctly.

    There are three main types of SIBO, classified by the gas the bacteria produce:

    • Hydrogen-dominant SIBO: Most common type; often linked to diarrhea-predominant symptoms.
    • Methane-dominant SIBO (also called IMO — intestinal methanogen overgrowth): Associated with constipation and slower gut motility.
    • Hydrogen sulfide SIBO: A newer, less understood type linked to diarrhea, fatigue, and a distinct sulfur-like odor in gas.

    Understanding which type you have matters because treatment protocols can differ. This is why working closely with a gastroenterologist is essential.

    If you’re curious about the broader ecosystem of bacteria in your digestive tract, our article on Gut Microbiome: What It Is and Why It Matters provides helpful background context.

    Signs and Symptoms of SIBO

    SIBO symptoms can range from mildly annoying to significantly disruptive. They often mimic other digestive conditions, which is one reason this condition goes undiagnosed for so long. Symptoms typically worsen after eating — particularly after meals high in carbohydrates or fiber — because bacteria rapidly ferment these foods.

    Early or mild symptoms may include:

    • Excessive bloating, especially after meals
    • Abdominal gas and flatulence
    • Stomach cramps or discomfort
    • Alternating diarrhea and constipation
    • A feeling of fullness shortly after eating
    • Nausea

    Advanced or more severe symptoms may include:

    • Chronic diarrhea or constipation
    • Unintentional weight loss
    • Nutrient deficiencies (especially vitamin B12, iron, and fat-soluble vitamins A, D, E, and K)
    • Fatigue and brain fog
    • Anemia
    • Osteoporosis over time due to poor calcium and vitamin D absorption
    • Fatty stools (steatorrhea) — pale, oily, or foul-smelling stools indicating fat malabsorption

    A 2020 review in the journal Nutrients confirmed that SIBO significantly impairs nutrient absorption, with vitamin B12 deficiency being particularly common because gut bacteria actually consume B12 before the body can use it.

    This variation in symptoms is one reason SIBO is so difficult to pin down. As always, individual presentation varies from person to person, and experiencing several of these symptoms doesn’t automatically mean you have SIBO — only proper testing can confirm a diagnosis.

    Causes and Risk Factors

    SIBO doesn’t develop randomly. Several underlying conditions and lifestyle factors can create the right environment for bacterial overgrowth in the small intestine.

    Structural or motility-related causes:

    • Slow gut motility: The migrating motor complex (MMC) is a wave of muscular contractions that sweeps bacteria out of the small intestine between meals. When this process is impaired — as in conditions like diabetes-related gastroparesis — bacteria can accumulate.
    • Anatomical abnormalities: Surgical scarring, bowel obstructions, or structural abnormalities can create pockets where bacteria pool.
    • Ileocecal valve dysfunction: This valve separates the small and large intestine. If it doesn’t close properly, colonic bacteria can backflow into the small intestine.

    Medical conditions strongly associated with SIBO:

    • Irritable bowel syndrome (IBS) — studies suggest SIBO is present in up to 84% of IBS patients
    • Celiac disease
    • Crohn’s disease
    • Type 2 diabetes with gastroparesis
    • Hypothyroidism (due to slowed gut motility)
    • Liver cirrhosis
    • Chronic pancreatitis
    • Scleroderma and other autoimmune conditions

    Lifestyle and medication-related risk factors:

    • Long-term use of proton pump inhibitors (PPIs), which reduce stomach acid that normally limits bacterial growth
    • Frequent antibiotic use, which disrupts gut flora balance
    • High-sugar, low-fiber diets that feed bacterial overgrowth
    • Chronic stress, which alters gut motility and immune function
    • Aging, as gut motility tends to slow with age

    According to the American College of Gastroenterology, adults over 60 are at significantly higher risk for SIBO due to slower intestinal transit time and more frequent use of acid-suppressing medications.

    Our in-depth guide on IBS: Symptoms, Causes, and Effective Treatment Options explores how these two conditions frequently overlap and reinforce each other.

    Diagnosis: What to Expect

    If your doctor suspects SIBO, the diagnostic process is typically straightforward, though no test is perfect. Here’s what you can expect.

    The Lactulose or Glucose Breath Test (most common)

    This is the most widely used, non-invasive test for SIBO. You drink a sugar solution (lactulose or glucose), and then breathe into collection bags at regular intervals over 2 to 3 hours. If bacteria in the small intestine ferment the sugar, they produce hydrogen and/or methane gas, which is detected in your breath. Elevated levels at early time points suggest SIBO.

    Clinical evidence indicates the lactulose breath test has a sensitivity of roughly 52 to 68 percent and a specificity of 83 to 86 percent, according to studies published in the Journal of Clinical Gastroenterology. It’s not a perfect test, but it’s widely accessible and avoids invasive procedures.

    Small intestinal aspirate and culture (gold standard)

    This involves passing a tube through your mouth into the small intestine to collect fluid, which is then cultured for bacterial growth. A count of more than 10³ colony-forming units per milliliter is considered diagnostic. While this is the most accurate method, it is invasive, expensive, and not routinely available in all clinical settings.

    Blood and stool tests

    Your doctor may also order blood tests to check for nutrient deficiencies (B12, iron, vitamin D, folate) and a comprehensive metabolic panel. Stool tests can sometimes reveal fat malabsorption but are not diagnostic for SIBO on their own.

    When to seek diagnosis: If you’ve experienced chronic bloating, unexplained gas, alternating bowel habits, or fatigue lasting more than a few weeks — especially after ruling out other causes — it’s appropriate to ask your doctor about SIBO testing.

    Treatment Options for SIBO

    Treatment for SIBO typically involves a combination of antibiotic therapy to reduce bacterial overgrowth, dietary modifications to starve remaining bacteria, and addressing the underlying condition driving the overgrowth. Without treating the root cause, SIBO often recurs.

    Antibiotic Therapy (first-line treatment)

    The most commonly prescribed antibiotic for SIBO is rifaximin (Xifaxan), a non-absorbable antibiotic that works locally in the gut without significantly affecting systemic bacteria. Clinical evidence from multiple randomized controlled trials, including a landmark study published in the New England Journal of Medicine, supports rifaximin as highly effective for hydrogen-dominant SIBO, with symptom relief in 40 to 70 percent of patients.

    For methane-dominant SIBO, research suggests a combination of rifaximin and neomycin may be more effective. Your physician will determine the appropriate approach based on your breath test results and symptom profile.

    Prokinetic Medications

    Because impaired gut motility is often a root cause, some physicians prescribe prokinetic agents — medications that help restore normal intestinal movement — after antibiotic treatment to reduce the risk of relapse. Low-dose naltrexone and low-dose erythromycin are among the options most physicians consider in this context.

    Elemental Diet

    An elemental diet involves consuming a liquid formula of pre-digested nutrients that are absorbed very early in the digestive tract, leaving little food for bacteria to ferment. Research suggests a 2-week elemental diet can normalize breath test results in approximately 80 percent of SIBO patients, though compliance is challenging due to palatability. This is typically reserved for cases where antibiotics haven’t worked or aren’t tolerated.

    Dietary Modifications (complementary, not standalone)

    Dietary changes are considered supportive therapy, not a replacement for medical treatment. The most clinically studied approach is the low-FODMAP diet (Fermentable Oligosaccharides, Disaccharides, Monosaccharides, and Polyols). This eating plan temporarily restricts certain carbohydrates that bacteria readily ferment, helping to reduce symptoms during and after treatment.

    Other dietary strategies physicians may discuss include:

    • Reducing simple sugars and refined carbohydrates
    • Eating smaller, more frequent meals
    • Spacing meals 4 to 5 hours apart to allow the MMC to sweep the gut between feedings
    • Avoiding eating late at night

    Probiotics: Proceed with Caution

    This is where many people get confused. While probiotics are often recommended for gut health broadly, research on their role in SIBO is mixed. Some studies suggest certain strains may worsen symptoms by adding more bacteria to an already overpopulated environment. Most physicians recommend waiting until after antibiotic treatment before introducing probiotics, and always under medical guidance.

    Living With SIBO and Preventing Recurrence

    One of the most challenging aspects of SIBO is its high recurrence rate. Studies estimate that 44 percent of patients experience a relapse within 9 months of treatment if the underlying cause is not addressed. The following strategies can help you manage your condition and reduce the risk of recurrence.

    Address the root cause. This is the single most important step. Whether it’s managing your hypothyroidism, adjusting your diabetes care, working with your physician to reassess long-term PPI use, or treating structural issues, resolving what allows SIBO to develop in the first place is essential for long-term success.

    Support gut motility. Clinical evidence indicates that regular physical activity helps maintain healthy intestinal transit time. Even a 20- to 30-minute walk after meals can stimulate digestive movement. Staying well-hydrated also supports peristalsis — the muscular contractions that move food through your gut.

    Practice mindful eating habits. Eating slowly, chewing thoroughly, and avoiding large meals all reduce the digestive burden on your small intestine. Research suggests that chronic stress impairs the MMC, so stress management techniques — including mindfulness, adequate sleep, and relaxation practices — may support gut motility over time. For related reading on managing stress and its gut-brain connection, see our guide on Adaptogens for Stress Management: An Evidence-Based Guide.

    Follow up with regular testing. If you’ve been treated for SIBO, your physician may recommend repeat breath testing 2 to 4 weeks after completing antibiotics to confirm eradication. Routine follow-up appointments allow for early detection of recurrence.

    Monitor for nutritional deficiencies. Because SIBO impairs absorption, regular blood panels checking vitamin B12, iron, ferritin, vitamin D, and folate are an important part of long-term management. Supplementation may be recommended based on your lab results.

    When to Call Your Doctor or Seek Emergency Care

    While most SIBO symptoms are uncomfortable but not life-threatening, certain signs require prompt medical attention.

    Contact your doctor soon if you experience:

    • Unexplained weight loss of more than 5 to 10 pounds over a few months
    • Persistent fatigue that doesn’t improve with rest
    • Ongoing diarrhea lasting more than 4 weeks
    • Symptoms that worsen during or after antibiotic treatment
    • Signs of nutritional deficiency (numbness in extremities, brittle nails, hair loss, or vision changes)

    Seek emergency care immediately if you experience:

    • Severe abdominal pain that comes on suddenly
    • High fever accompanied by abdominal symptoms
    • Blood in your stool or black, tarry stools
    • Signs of dehydration: extreme thirst, decreased urination, dizziness, or rapid heart rate
    • Vomiting that prevents you from keeping fluids down

    These symptoms may indicate a more serious condition such as bowel obstruction, severe infection, or inflammatory bowel disease, and require immediate evaluation.

    What to tell your doctor at your next visit: Keep a symptom diary noting when symptoms occur, what you ate beforehand, how long they last, and what seems to make them better or worse. This information is invaluable for your physician in building an accurate clinical picture.

    Frequently Asked Questions About SIBO

    Q: Can SIBO go away on its own without treatment?
    In rare cases, resolving an underlying cause (such as treating hypothyroidism) may reduce SIBO symptoms without direct antibiotic treatment. However, most gastroenterologists recommend confirmed antibiotic therapy because untreated SIBO can lead to progressive nutrient deficiencies and worsening gut function over time. Self-treatment without medical supervision is not recommended.

    Q: Is SIBO the same as IBS?
    No, but they are closely linked. IBS is a clinical diagnosis based on symptom patterns, while SIBO is a condition identified through testing. Research suggests a substantial overlap — many people diagnosed with IBS may actually have SIBO driving their symptoms. Your physician can order breath testing to help differentiate the two. For more on IBS, see our full article on IBS: Symptoms, Causes, and Effective Treatment Options.

    Q: How long does SIBO treatment take?
    Standard antibiotic treatment for SIBO typically lasts 10 to 14 days, depending on the type of SIBO and the regimen prescribed. Some cases require repeated courses. Full symptom resolution may take several weeks to months as the gut heals and dietary adjustments are made. Individual response varies significantly.

    Q: Can diet alone treat SIBO?
    Diet alone is generally not sufficient to eradicate SIBO, though dietary changes can reduce symptoms and support recovery. The elemental diet has the strongest evidence of any dietary approach, but it is considered a medical intervention and should be used under physician supervision. Most clinical guidelines recommend combining dietary modification with antibiotic therapy.

    Q: Is SIBO contagious?
    No. SIBO is not contagious. It results from an imbalance in your own gut bacteria, typically driven by underlying health conditions, structural factors, or motility problems — not from exposure to another person. You cannot “catch” SIBO from someone else.

    Conclusion

    SIBO is a real, diagnosable, and treatable condition — not just “stress” or an overactive imagination. For people like David who have struggled with chronic digestive symptoms for months or years, getting an accurate diagnosis can be genuinely life-changing.

    With the right combination of antibiotic therapy, dietary support, motility management, and addressing the root cause, most people experience meaningful improvement. The key is not to go it alone. Work with a qualified gastroenterologist or primary care physician who can guide your diagnosis and treatment plan based on your specific type of SIBO and underlying health profile.

    Your gut health matters deeply to your overall well-being — and with the right medical support, reclaiming it is absolutely within reach.


    Medical Disclaimer: This article is for informational and educational purposes only. It does not constitute medical advice, diagnosis, or treatment. Always consult your physician or a qualified healthcare provider before making changes to your health routine or treatment plan.

    Medically reviewed by our editorial health team. Content follows evidence-based standards aligned with CDC and NIH guidelines.
  • Leaky Gut Syndrome: Symptoms, Causes & Treatment

    Leaky Gut Syndrome: Symptoms, Causes & Treatment

    Leaky Gut Syndrome: Symptoms, Causes and Treatment Options

    Understanding intestinal permeability may be the missing piece in your digestive health puzzle.

    Marcus, 47, had been dealing with bloating, fatigue, and unexplained joint pain for nearly two years. He had seen three different specialists, ruled out Crohn’s disease and celiac disease, and still had no clear answers. It was not until his gastroenterologist mentioned the concept of increased intestinal permeability — commonly called leaky gut syndrome — that the pieces finally started to come together.

    If that story sounds familiar, you are not alone. Research published through the National Institutes of Health estimates that gut barrier dysfunction plays a contributing role in a wide range of inflammatory and autoimmune conditions affecting tens of millions of Americans. Yet despite growing clinical interest, leaky gut syndrome remains one of the most misunderstood topics in modern medicine.

    In this guide, you will learn what leaky gut syndrome actually is, what the science says about its causes and symptoms, how it is diagnosed, and what evidence-based treatment options are available today. Whether you are managing a chronic condition or simply trying to protect your long-term digestive health, this article will give you the grounded, practical information you need to have a productive conversation with your doctor.

    What Is Leaky Gut Syndrome?

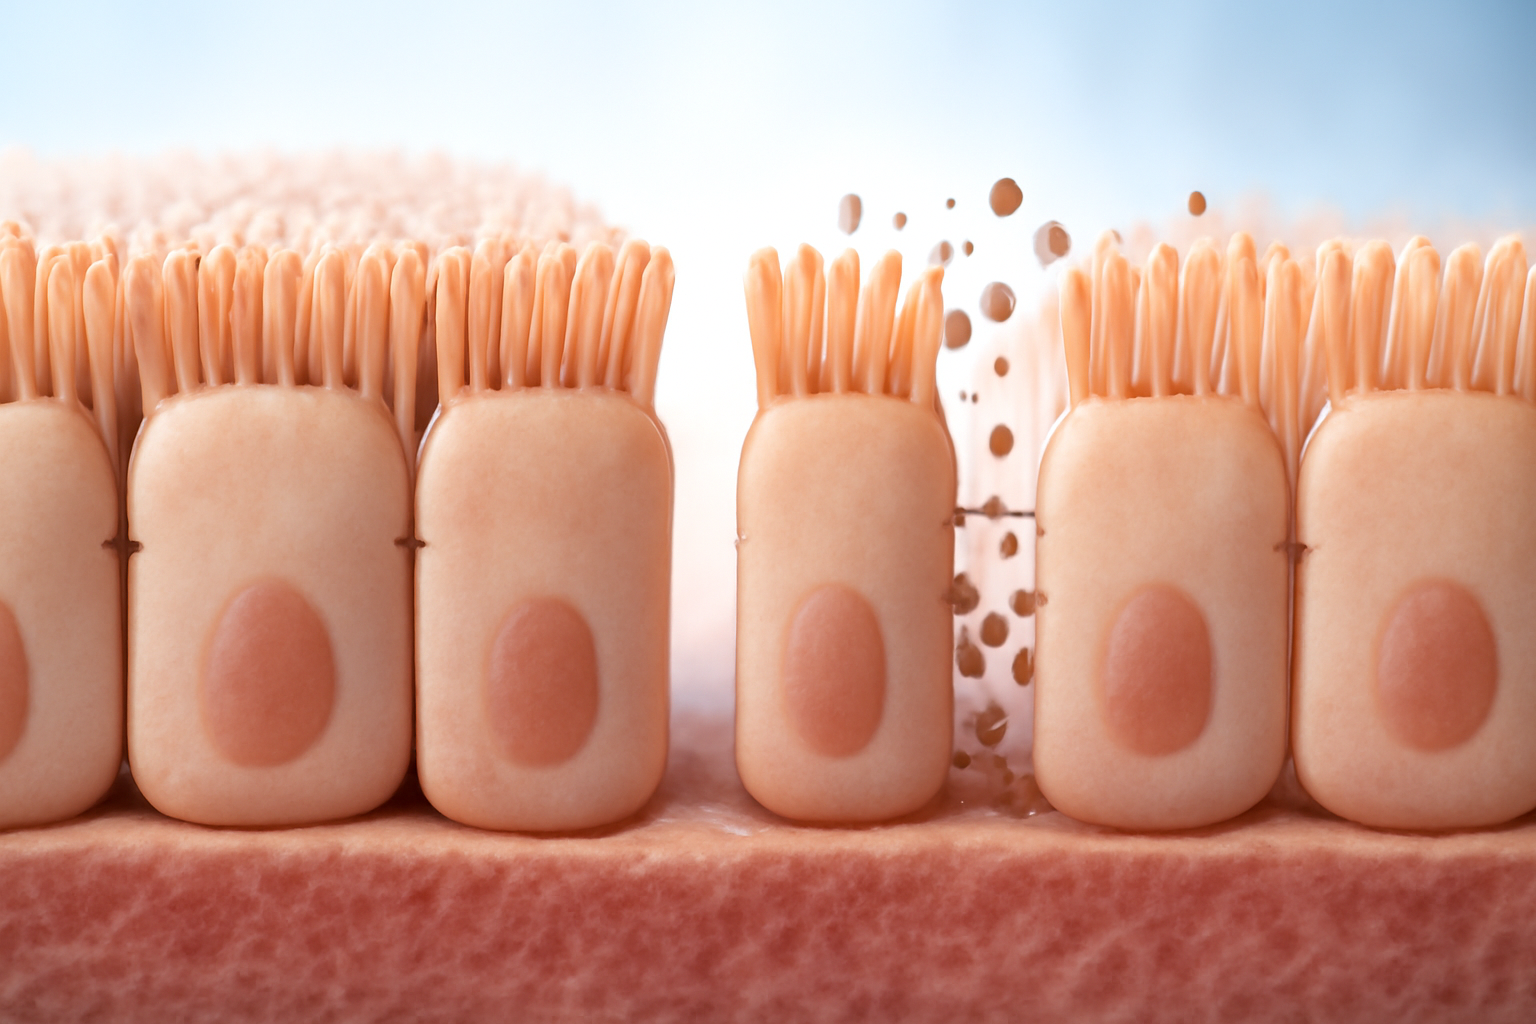
    Your digestive tract is lined with a single layer of epithelial cells — specialized cells that act as a selective barrier between the contents of your intestines and your bloodstream. This lining is held together by tight junction proteins, which function somewhat like the mortar between bricks, controlling what passes through and what stays out.

    When these tight junctions become compromised, the intestinal barrier loses its selectivity. Partially digested food particles, bacterial toxins, and other substances that would normally remain inside the gut can pass into the bloodstream. This process is what clinicians refer to as increased intestinal permeability — or, in more colloquial terms, leaky gut syndrome.

    It is important to clarify one thing: leaky gut syndrome is not yet recognized as a formal standalone diagnosis in mainstream clinical practice. However, intestinal permeability itself is a well-documented, measurable physiological phenomenon. According to research from the NIH’s National Institute of Diabetes and Digestive and Kidney Diseases, disrupted gut barrier function is increasingly linked to conditions ranging from inflammatory bowel disease to metabolic disorders and even certain autoimmune diseases.

    This distinction matters because it separates the legitimate science from the oversimplified or exaggerated claims you may encounter online. Increased intestinal permeability is real, measurable, and clinically relevant — but it is typically a contributing factor within a larger health picture, not an isolated diagnosis on its own.

    Signs and Symptoms of Leaky Gut

    One of the most challenging aspects of leaky gut syndrome is that its symptoms overlap significantly with many other gastrointestinal and systemic conditions. This is precisely why it often goes unrecognized for years.

    Early and Common Symptoms:

    • Chronic bloating, especially after meals
    • Abdominal cramping or discomfort
    • Irregular bowel habits — diarrhea, constipation, or alternating between both
    • Persistent fatigue that is not explained by sleep issues
    • Brain fog or difficulty concentrating
    • Food sensitivities that seem to be worsening over time
    • Skin issues such as eczema, acne, or unexplained rashes

    Symptoms That May Suggest a More Advanced Problem:

    • Joint pain and inflammation without a clear orthopedic cause
    • Frequent infections or a weakened immune response
    • Mood disturbances including anxiety and depression
    • Nutritional deficiencies despite an adequate diet
    • Autoimmune flare-ups in conditions like rheumatoid arthritis or Hashimoto’s thyroiditis

    A 2021 review published in Frontiers in Immunology found that patients with documented increased intestinal permeability showed elevated levels of lipopolysaccharides (LPS) — bacterial endotoxins — in their bloodstream, which correlated with systemic inflammation markers. This gives clinicians a measurable window into how gut barrier dysfunction can drive symptoms far beyond the digestive tract.

    This variation is important to understand: not every person with intestinal permeability will experience the same constellation of symptoms. This varies significantly from person to person depending on genetics, existing health conditions, and overall microbiome health.

    Causes and Risk Factors

    The gut barrier does not break down overnight. Research suggests it is typically the result of multiple overlapping factors that accumulate over months or years. Understanding these causes is critical because many of them are modifiable through lifestyle changes and medical management.

    Dietary Factors:

    • Diets high in ultra-processed foods, refined sugars, and artificial emulsifiers have been shown in multiple animal and human studies to disrupt tight junction proteins
    • Chronic alcohol consumption is one of the most well-documented dietary contributors to increased intestinal permeability, according to research from the NIH’s National Institute on Alcohol Abuse and Alcoholism
    • Low dietary fiber intake reduces the production of short-chain fatty acids, which are essential for maintaining the intestinal lining

    Medications:

    • Long-term use of non-steroidal anti-inflammatory drugs (NSAIDs) such as ibuprofen and aspirin has been associated with gut barrier disruption in multiple clinical studies
    • Proton pump inhibitors (PPIs), when used chronically, may alter gut microbiome composition in ways that affect barrier integrity
    • Antibiotics, while medically necessary, can deplete beneficial gut bacteria that help maintain the intestinal lining

    Chronic Stress: The gut-brain axis — the bidirectional communication network between your brain and digestive system — means that chronic psychological stress directly affects gut motility and barrier function. Clinical evidence from the American Psychological Association indicates that stress hormones like cortisol can weaken tight junction proteins over time.

    Underlying Conditions: Conditions such as celiac disease, Crohn’s disease, irritable bowel syndrome (IBS), and type 1 diabetes have all been independently associated with measurable increases in intestinal permeability. In some cases, researchers are still working to determine whether the permeability is a cause or a consequence of the condition.

    According to the CDC, approximately 60 million Americans are affected by some form of digestive disease — a statistic that underscores just how widespread gut barrier issues may be across the US population.

    Diagnosis: What to Expect

    If you suspect you may have issues with intestinal permeability, the first step is a thorough evaluation by your primary care physician or a board-certified gastroenterologist. There is no single universally accepted test for leaky gut syndrome, which is part of why diagnosis requires a comprehensive clinical approach.

    Tests Your Doctor May Order:

    • Lactulose-mannitol urine test: This is the most widely used research tool for measuring intestinal permeability. You drink a solution containing two sugars, and their ratio in your urine indicates how permeable your gut lining is. While used extensively in research, it is not yet standardized for routine clinical practice at all facilities.
    • Zonulin blood test: Zonulin is a protein that regulates tight junctions. Elevated serum zonulin levels have been associated with increased permeability in studies published in journals affiliated with Mayo Clinic research teams. However, test standardization is still an active area of development.
    • Comprehensive stool analysis: This can evaluate microbiome diversity, markers of inflammation (such as calprotectin), and signs of dysbiosis — an imbalance in gut bacteria — that may accompany barrier dysfunction.
    • Standard gastrointestinal workup: Your doctor will likely also order bloodwork to check for inflammatory markers like CRP (C-reactive protein), complete metabolic panels, and potentially endoscopy to rule out conditions like Crohn’s disease or ulcerative colitis.

    Most physicians recommend seeking evaluation if you have been experiencing persistent unexplained gastrointestinal symptoms for more than four to six weeks, particularly if accompanied by systemic symptoms like fatigue or joint pain.

    Treatment Options

    Treatment for increased intestinal permeability is most effective when it addresses the underlying causes rather than just managing symptoms. Clinical evidence supports a multimodal approach combining medical care with targeted lifestyle modifications.

    Medical Treatments:

    • Treating underlying conditions: If a diagnosed condition such as celiac disease, IBD, or SIBO (small intestinal bacterial overgrowth) is driving the permeability, treating that condition is the primary medical priority
    • Targeted antimicrobials: When dysbiosis or SIBO is identified, a gastroenterologist may prescribe specific antibiotic or antifungal therapy to rebalance gut flora
    • Medication review: Your doctor may assess whether any current medications are contributing to gut barrier issues and discuss alternatives where appropriate

    Dietary Approaches: A 2023 randomized controlled trial published through NIH-affiliated research showed that a diet rich in fermented foods — including yogurt, kefir, kimchi, and sauerkraut — significantly increased microbiome diversity and reduced inflammatory markers compared to a high-fiber diet alone. Research suggests the following dietary strategies support gut barrier integrity:

    • Increasing dietary fiber from whole fruits, vegetables, legumes, and whole grains to fuel short-chain fatty acid production
    • Reducing ultra-processed food intake and refined sugars
    • Limiting or eliminating alcohol, particularly during an active treatment period
    • Following a gluten-free diet if celiac disease or confirmed gluten sensitivity is present

    Probiotics and Supplements: Clinical evidence indicates that specific probiotic strains — particularly Lactobacillus rhamnosus GG and Bifidobacterium longum — may help restore gut barrier function. A meta-analysis from the American Journal of Clinical Nutrition found that probiotic supplementation was associated with reduced intestinal permeability markers in patients with IBS and inflammatory bowel conditions. L-glutamine, a conditionally essential amino acid, has also shown promise in early clinical research as a support for intestinal lining repair. Always discuss any supplement regimen with your healthcare provider before starting.

    Stress Management: Given the documented connection between the gut-brain axis and barrier function, evidence-based stress reduction techniques — including cognitive behavioral therapy (CBT), mindfulness-based stress reduction (MBSR), and regular aerobic exercise — are increasingly considered integral components of gut health treatment by gastroenterologists and integrative medicine physicians.

    Living With Gut Permeability Issues and Long-Term Prevention

    Managing a compromised gut barrier is not a quick fix. Most physicians and researchers agree that meaningful, lasting improvement typically requires sustained lifestyle changes maintained over months, not days.

    Practical Daily Strategies:

    • Aim for at least 25-38 grams of dietary fiber per day, as recommended by the Academy of Nutrition and Dietetics
    • Eat slowly and mindfully — eating too quickly reduces digestive enzyme activation and increases fermentation and bloating
    • Prioritize sleep: research from Harvard Medical School suggests that chronic sleep deprivation alters gut microbiome composition within just two weeks
    • Stay physically active: moderate aerobic exercise has been shown to increase microbiome diversity and support gut barrier integrity in studies from the Cleveland Clinic
    • Limit NSAID use to the minimum medically necessary, and discuss alternatives with your doctor if you rely on them regularly
    • Stay adequately hydrated — water supports mucus layer production in the gut, which forms the first line of defense for the intestinal epithelium

    For prevention, research suggests that the same lifestyle factors that protect cardiovascular health — a fiber-rich diet, regular exercise, stress management, and limited alcohol — also maintain a resilient gut barrier. These are not separate health goals; they are deeply interconnected.

    When to Call Your Doctor and Emergency Red Flags

    While leaky gut syndrome itself is rarely a medical emergency, certain symptoms associated with gut dysfunction require prompt medical attention.

    Call your doctor promptly if you experience:

    • Persistent diarrhea lasting more than two weeks
    • Unexplained and significant weight loss
    • Blood in your stool or rectal bleeding
    • Severe abdominal pain that is constant or progressively worsening
    • Symptoms of nutritional deficiency such as hair loss, extreme fatigue, or neurological changes

    Seek emergency care immediately if you experience:

    • Sudden, severe abdominal pain with fever and rigid abdomen — this may indicate bowel perforation or sepsis
    • Signs of significant blood loss: dizziness, rapid heartbeat, fainting, or large amounts of blood in stool
    • High fever accompanied by severe abdominal symptoms

    At your next routine visit, consider discussing your gut health history with your physician, including any long-term medication use, dietary patterns, and the full range of symptoms you have been experiencing. Bring a written list — your doctor will appreciate the detail and it ensures nothing is overlooked.

    Frequently Asked Questions

    Is leaky gut syndrome a real medical diagnosis?
    Increased intestinal permeability is a real, measurable physiological phenomenon supported by peer-reviewed research. However, "leaky gut syndrome" is not currently listed as a formal standalone diagnosis in standard medical classification systems like the ICD-10. Most gastroenterologists evaluate it as a contributing mechanism within a broader clinical picture rather than a primary diagnosis.

    Can leaky gut be permanently healed?
    Research suggests that gut barrier function can significantly improve with the right combination of medical treatment, dietary changes, and lifestyle modifications. However, "permanently healed" is not the most accurate framing — maintaining a healthy gut barrier is an ongoing process, much like maintaining cardiovascular health. Clinical evidence indicates that individuals who sustain dietary and lifestyle changes see the most durable improvements.

    What foods are worst for intestinal permeability?
    Clinical evidence points most strongly to ultra-processed foods, refined sugars, artificial emulsifiers (found in many packaged foods), and alcohol as the most disruptive to gut barrier integrity. For individuals with confirmed celiac disease, gluten is also a significant factor. Your specific triggers may vary, which is why working with a registered dietitian alongside your physician is valuable.

    Do probiotics actually help with leaky gut?
    The evidence is promising but still evolving. Certain probiotic strains have shown measurable benefits for intestinal permeability markers in clinical trials, particularly in individuals with IBS or inflammatory bowel conditions. However, not all probiotics are the same — strain selection, dosage, and the individual's existing microbiome all affect outcomes. Your doctor or a registered dietitian can help you evaluate options appropriate for your situation.

    Can stress alone cause leaky gut?
    Chronic stress is a documented contributor to gut barrier disruption via the gut-brain axis. Research published through NIH-affiliated studies shows that prolonged elevation of stress hormones like cortisol and corticotropin-releasing hormone (CRH) can directly weaken tight junction proteins. That said, stress typically acts as one factor among several — rarely the sole cause in isolation.

    Conclusion

    Leaky gut syndrome — or increased intestinal permeability — sits at a fascinating and important intersection of digestive health, immune function, and systemic wellness. The science is real and growing, even if the clinical picture is still being refined by researchers at institutions like the NIH, Mayo Clinic, and Cleveland Clinic.

    The encouraging reality is that many of the factors contributing to gut barrier dysfunction are modifiable. A thoughtful combination of evidence-based dietary changes, appropriate medical treatment, stress management, and consistent follow-up with your healthcare team can lead to meaningful improvement in gut health and overall wellbeing.

    Do not try to navigate this on your own. If you recognize yourself in these symptoms, bring this article as a starting point to your next doctor's appointment. You deserve answers — and with the right clinical support, they are within reach.


    Medical Disclaimer: This article is for informational and educational purposes only. It does not constitute medical advice, diagnosis, or treatment. Always consult your physician or a qualified healthcare provider before making changes to your health routine or treatment plan.

    Medically reviewed by our editorial health team. Content follows evidence-based standards aligned with CDC and NIH guidelines.