
Category: Women’s Health

Explore trusted information about women’s health, hormonal balance, reproductive wellness, nutrition, and preventive care.

  • Hormonal Imbalance in Women After 40: Signs & Solutions

    Hormonal Imbalance in Women After 40: Signs & Solutions

    Your hormones don’t just change during menopause — they begin shifting years earlier, quietly reshaping how you feel every single day.

    At 44, Michelle had always considered herself a healthy, energetic woman. Then, almost overnight, she started waking at 3 a.m. drenched in sweat, snapping at her kids over nothing, and gaining weight around her midsection despite eating the same way she had for years. Her doctor ran some routine labs, sat down with her, and said four words she hadn’t expected: hormonal imbalance after 40.

    She wasn’t alone. According to the Office on Women’s Health (a division of the U.S. Department of Health and Human Services), hormone-related symptoms affect the vast majority of women during the perimenopause transition — a phase that can begin as early as the late 30s or early 40s. Yet many women dismiss their symptoms as stress, aging, or burnout — delaying care by months or even years.

    This guide will help you understand what hormonal imbalance in women after 40 actually means, what’s happening in your body, how it’s diagnosed, and what evidence-based options exist to help you feel like yourself again.

    What Is Hormonal Imbalance in Women After 40?

    Hormonal imbalance refers to a disruption in the normal levels of one or more hormones circulating in the bloodstream. In women over 40, this most commonly involves estrogen, progesterone, testosterone, cortisol, thyroid hormones, and insulin — all of which interact in complex ways.

    The most well-known driver is the transition toward menopause. According to the NIH’s National Institute on Aging, the average age of menopause in the U.S. is 51 — but the hormonal changes leading up to it (perimenopause) typically begin 4 to 10 years earlier. That means millions of women in their early 40s are already navigating significant hormonal shifts.

    But perimenopause isn’t the only cause. Thyroid disorders, adrenal dysfunction, insulin resistance, and chronic stress can all create or worsen hormonal imbalance — independent of reproductive aging. The CDC estimates that 20 million Americans have thyroid disease, and women are 5 to 8 times more likely than men to develop it.

    Understanding which hormones are involved — and why — is the first step to getting targeted, effective care.

    Signs and Symptoms of Hormonal Imbalance

    One reason hormonal imbalance is so often missed is that its symptoms are remarkably diverse. They can mimic depression, anxiety, chronic fatigue, or even heart disease. Clinical evidence from the North American Menopause Society confirms that estrogen fluctuations alone can affect more than 30 organ systems in the female body.

    Early Signs (commonly appear in the 40s):

    • Irregular or heavier menstrual cycles
    • Increased PMS symptoms (bloating, mood changes, breast tenderness)
    • Difficulty falling or staying asleep
    • Unexplained fatigue even after a full night’s rest
    • Mild anxiety or irritability that feels new or out of proportion
    • Brain fog or difficulty concentrating
    • Weight gain, especially around the abdomen
    • Reduced sex drive
    • Mild hair thinning

    More Advanced or Persistent Signs:

    • Hot flashes and night sweats
    • Vaginal dryness or discomfort during intercourse
    • Significant mood shifts, including depressive episodes
    • Bone density loss (often asymptomatic until a fracture occurs)
    • Elevated fasting blood sugar or prediabetes markers
    • Worsening acne or dry, thinning skin
    • Heart palpitations

    This varies from person to person. Some women experience only mild symptoms; others find their quality of life significantly disrupted. The pattern and severity often depend on which hormones are involved and by how much they’ve shifted.

    Causes and Risk Factors

    Hormonal imbalance in women over 40 rarely has a single cause. Research suggests it typically results from a combination of biological, lifestyle, and environmental factors.

    Biological Causes:

    • Perimenopause and ovarian aging: As ovarian reserve declines, estrogen and progesterone production becomes erratic before eventually dropping substantially.
    • Thyroid dysfunction: Hypothyroidism (underactive thyroid) is particularly common in women over 40 and can amplify nearly every symptom of hormonal imbalance — fatigue, weight gain, mood changes, and hair loss included.
    • Adrenal fatigue and cortisol dysregulation: Chronic psychological or physical stress keeps cortisol elevated, which can suppress progesterone production and interfere with thyroid signaling.
    • Insulin resistance: Estrogen plays a role in insulin sensitivity. As estrogen declines, many women become more insulin-resistant — raising the risk of weight gain and type 2 diabetes.

    Lifestyle Risk Factors:

    • Chronic sleep deprivation (fewer than 7 hours consistently)
    • High-sugar, ultra-processed diets
    • Sedentary behavior
    • Chronic psychological stress
    • Alcohol consumption (which disrupts estrogen metabolism)
    • Smoking

    Environmental Factors:

    • Exposure to endocrine-disrupting chemicals (EDCs) found in certain plastics (BPA), pesticides, and personal care products. The National Institute of Environmental Health Sciences has flagged EDCs as a significant concern for women’s hormonal health.

    A family history of early menopause, thyroid disease, PCOS, or autoimmune conditions also increases your risk.

    Diagnosis: What to Expect

    If you suspect hormonal imbalance, your first step is a thorough conversation with your primary care physician or a gynecologist. Clinical diagnosis typically involves a combination of symptom review, medical history, and laboratory testing.

    Common Lab Tests Your Doctor May Order:

    • FSH (follicle-stimulating hormone): Elevated FSH is one of the primary markers used to assess proximity to menopause.
    • Estradiol: Measures circulating estrogen levels.
    • Progesterone: Often tested in the second half of the menstrual cycle to assess luteal phase adequacy.
    • TSH (thyroid-stimulating hormone) and free T4/T3: To rule out thyroid dysfunction, which is frequently overlooked.
    • Testosterone (total and free): Low testosterone affects libido, energy, and mood in women too.
    • Fasting glucose and insulin: To assess insulin resistance.
    • DHEA-S and cortisol: If adrenal involvement is suspected.

    Most physicians recommend seeking evaluation when symptoms persist for more than 4 to 6 weeks, are worsening, or are meaningfully affecting your daily functioning and quality of life. The sooner you seek a diagnosis, the more targeted your treatment can be.

    If you’ve also noticed changes in urinary habits alongside hormonal symptoms, it may be worth reviewing our guide on Bladder Health in Women After 40, as these systems are closely connected through estrogen signaling.

    Treatment Options

    Treatment for hormonal imbalance in women over 40 is not one-size-fits-all. Most physicians recommend a layered approach that begins with lifestyle modifications and, depending on severity and lab findings, may include hormonal or non-hormonal medical therapies.

    Conventional Medical Treatments:

    Hormone Therapy (HT): Once controversial, hormone therapy has been significantly rehabilitated by updated clinical evidence. The Menopause Society (formerly the North American Menopause Society) now affirms that for healthy women under 60 or within 10 years of menopause onset, the benefits of HT typically outweigh the risks — particularly for managing hot flashes, sleep disruption, bone loss, and vaginal symptoms. HT comes in various forms (patches, gels, pills, vaginal rings), and the right formulation depends on your individual health history.

    Thyroid Medication: If hypothyroidism is confirmed, your doctor may prescribe levothyroxine to normalize thyroid function. Clinical evidence from Mayo Clinic indicates that treating thyroid dysfunction can dramatically improve energy, mood, weight, and cognitive clarity in affected women.

    Non-Hormonal Prescription Options: For women who cannot or prefer not to use hormone therapy, several FDA-approved non-hormonal options exist for specific symptoms — including certain antidepressants (SSRIs and SNRIs) for hot flashes, and fezolinetant (a newer neurokinin receptor antagonist approved in 2023) for vasomotor symptoms.

    Lifestyle Modifications (Evidence-Based Complements):

    • Exercise: Research published in the journal Menopause found that regular aerobic and resistance training significantly reduces hot flash frequency, improves insulin sensitivity, and supports bone density. Most physicians recommend 150 minutes of moderate-intensity activity per week.
    • Dietary changes: A Mediterranean-style diet rich in phytoestrogens (flaxseed, soy), fiber, lean protein, and anti-inflammatory fats supports hormonal regulation. Reducing refined sugars and alcohol is especially important.
    • Sleep hygiene: Prioritizing 7–9 hours and managing night sweats (cooler room temperature, moisture-wicking bedding, layered clothing) helps stabilize cortisol patterns.
    • Stress management: Chronic stress elevates cortisol, which directly competes with progesterone and worsens hormonal imbalance. Mindfulness-based stress reduction (MBSR) has clinical support for symptom relief in perimenopausal women.

    Supplements like magnesium, vitamin D, and omega-3 fatty acids may provide additional support, but should always be discussed with your doctor before starting — especially alongside prescription medications. For a deeper look at how magnesium specifically supports the nervous system and hormonal health, see our article on Magnesium Glycinate for Anxiety and Nervous System Support.

    Living With Hormonal Imbalance: Daily Management and Prevention

    Managing hormonal imbalance is a long-term commitment — not a short-term fix. Clinical evidence suggests that consistent daily habits have a compounding effect on hormonal stability over time.

    Practical Strategies That Make a Meaningful Difference:

    • Track your symptoms: Keeping a daily log of mood, sleep, menstrual cycle, energy, and hot flashes gives your doctor invaluable data and helps identify patterns or triggers.
    • Limit endocrine disruptors: Choose glass or stainless steel over plastic food containers, filter your drinking water, and read ingredient labels on personal care products. The NIH recommends minimizing BPA, phthalates, and parabens when possible.
    • Prioritize bone health: Estrogen decline accelerates bone loss. The National Osteoporosis Foundation recommends adequate calcium (1,200 mg/day for women over 50) and vitamin D, along with weight-bearing exercise, as preventive cornerstones.
    • Stay consistent with follow-up labs: Hormone levels fluctuate. Annual or biannual lab reviews help your doctor fine-tune your treatment plan over time.
    • Build a support network: Isolation worsens anxiety and depressive symptoms that often accompany hormonal shifts. Group support — whether in-person or online — has demonstrated psychological benefit in multiple clinical studies.

    Prevention isn’t always possible when biology is the primary driver, but lifestyle choices made in your 30s and 40s can meaningfully soften the hormonal curve and reduce your risk of long-term complications like osteoporosis and cardiovascular disease.

    When to Call Your Doctor — Emergency Signs

    Most hormonal imbalance symptoms are manageable in a primary care or gynecology setting. However, certain signs require prompt medical attention.

    Seek urgent or emergency care if you experience:

    • Chest pain, shortness of breath, or heart palpitations that are sudden or severe
    • Sudden severe headache, visual disturbances, or one-sided weakness (possible stroke warning signs — estrogen fluctuations can transiently affect clotting and vascular tone)
    • Heavy vaginal bleeding soaking more than one pad per hour for two or more consecutive hours
    • Signs of deep depression including thoughts of self-harm — hormonal shifts can trigger or worsen mood disorders
    • Sudden significant weight loss, extreme fatigue, or a large neck swelling (possible thyroid crisis)

    Schedule a non-emergency appointment soon if you notice:

    • Symptoms that have persisted for more than 6 weeks and are worsening
    • New or changing irregular bleeding patterns
    • Significant mood changes that are affecting relationships or work
    • Bone fracture from a minor injury (possible osteoporosis red flag)

    When you call, be as specific as possible. Tell your doctor the duration of symptoms, their frequency, and how they affect your daily life. Bring your symptom log if you’ve kept one.

    Frequently Asked Questions

    1. Can hormonal imbalance cause weight gain even if I haven’t changed my diet?

    Yes. Research suggests that declining estrogen alters fat distribution, often shifting it toward the abdomen. Simultaneously, insulin resistance tends to increase, making it easier to store fat and harder to burn it — even without dietary changes. This is a common and legitimate concern, not a matter of willpower.

    2. How do I know if it’s hormonal imbalance or just stress or anxiety?

    Symptoms can overlap significantly. The most reliable way to distinguish them is through lab testing paired with a thorough clinical history. Stress and hormonal imbalance also frequently coexist and can worsen each other, so addressing both is often necessary for meaningful relief.

    3. Is hormone therapy safe for women over 40?

    For most healthy women under 60 who are within 10 years of menopause onset, current clinical evidence — including updated guidelines from The Menopause Society — supports hormone therapy as a safe and effective option for symptom management. Individual risk factors, including personal or family history of certain cancers or clotting disorders, must always be evaluated by your physician.

    4. Can I test my hormones at home?

    Several at-home hormone testing kits are now commercially available. While they can provide general directional information, they are not a substitute for clinical lab testing and physician interpretation. Hormone levels fluctuate throughout the day and menstrual cycle, and accurate diagnosis requires context that a home kit cannot provide alone.

    5. Will hormonal symptoms go away on their own after menopause?

    Some symptoms, like hot flashes, do tend to lessen naturally over time — often within 4 to 7 years, though a subset of women experience them for a decade or longer, according to the NIH. Other effects of estrogen decline, such as bone density loss and vaginal atrophy, are progressive without treatment. This is why proactive management — rather than a wait-and-see approach — is typically recommended by most physicians.

    Conclusion

    Hormonal imbalance in women after 40 is not just an inconvenience to be endured — it’s a real, measurable physiological shift that deserves clinical attention and compassionate care. The good news is that effective, evidence-based tools exist: from medical therapies tailored to your individual profile, to lifestyle habits that can meaningfully support your body through this transition.

    You don’t have to accept feeling exhausted, anxious, or unlike yourself as simply part of getting older. With the right information and the right healthcare partner, most women find a path back to stable energy, better sleep, and improved quality of life. Start the conversation with your doctor today — armed with your symptoms, your questions, and a willingness to advocate for your own health.

    This article is for informational and educational purposes only. It does not constitute medical advice, diagnosis, or treatment. Always consult your physician or a qualified healthcare provider before making changes to your health routine or treatment plan.

    Medically reviewed by our editorial health team. Content follows evidence-based standards aligned with CDC and NIH guidelines.


  • Bladder Health in Women After 40: Symptoms, Causes & Solutions

    Bladder Health in Women After 40: Symptoms, Causes & Solutions

    Bladder problems affect millions of American women — but most suffer in silence, assuming it’s just a normal part of aging.

    Linda, 52, had started planning her errands around bathroom locations. A sudden urge to urinate would strike without warning, and she’d already had a few close calls. She assumed this was just what getting older felt like — something to manage quietly, not discuss with her doctor. She was wrong on both counts.

    According to the National Institutes of Health (NIH), overactive bladder and urinary incontinence affect an estimated 33 million Americans, with women experiencing these conditions at nearly twice the rate of men. After age 40, hormonal shifts, pelvic floor changes, and other physiological transitions make women increasingly vulnerable to bladder dysfunction — yet fewer than half ever seek treatment.

    This guide will help you understand what’s happening with your bladder health after 40, why it happens, what symptoms are common versus concerning, and what evidence-based options exist to help you feel confident and in control again.

    What Is Bladder Health — and Why Does It Change After 40?

    Your bladder is a hollow, muscular organ that stores urine produced by your kidneys. A healthy bladder holds between 1.5 and 2 cups of fluid before signaling the urge to urinate. The process involves a complex coordination between the bladder muscle (called the detrusor), the pelvic floor muscles, and the nervous system.

    After age 40, several changes begin to affect this system. Estrogen — a hormone that plays a critical role in maintaining the tissue lining of the bladder and urethra — begins to decline in perimenopause and drops significantly after menopause. This hormonal shift can thin the urethral lining, reduce muscle tone in the pelvic floor, and make the bladder more sensitive and reactive.

    According to the American Urological Association, urinary incontinence — the involuntary leakage of urine — affects approximately 25 to 45 percent of women, with prevalence rising sharply after age 40. Despite how common it is, bladder dysfunction is consistently undertreated because many women are embarrassed to raise the topic with their healthcare provider.

    Understanding your bladder health is not just about comfort. Chronic bladder issues can affect sleep, mental health, social engagement, and overall quality of life in significant ways.

    Signs and Symptoms: What’s Common and What’s a Red Flag

    Bladder symptoms in women over 40 exist on a spectrum. Some are common and manageable with lifestyle changes; others may signal a condition requiring prompt medical evaluation.

    Common early symptoms include:

    • Increased frequency of urination (more than 8 times per day)
    • Urgency — a sudden, strong need to urinate that’s difficult to delay
    • Stress incontinence — leaking urine when you cough, sneeze, laugh, or exercise
    • Nocturia — waking up one or more times per night to urinate
    • A feeling that your bladder doesn’t fully empty after urinating
    • Mild pelvic pressure or discomfort

    More advanced or concerning symptoms include:

    • Urge incontinence — inability to reach the bathroom in time
    • Persistent pelvic or lower abdominal pain
    • Blood in the urine (hematuria) — always a red flag
    • Recurrent urinary tract infections (three or more per year)
    • Pain or burning during urination that doesn’t resolve
    • Difficulty initiating urination

    A 2022 study published in the journal Urology found that women with overactive bladder symptoms reported significantly higher rates of depression, anxiety, and sleep disturbance compared to women without bladder issues — underscoring the importance of taking these symptoms seriously rather than normalizing them.

    Causes and Risk Factors

    Bladder changes in women after 40 are rarely caused by a single factor. Most cases involve a combination of hormonal, structural, and lifestyle influences.

    Hormonal changes: The decline in estrogen during perimenopause and menopause is one of the most significant drivers. Estrogen helps maintain the strength and elasticity of the urethra and bladder tissue. Without adequate estrogen, the urethral lining thins — a condition sometimes called genitourinary syndrome of menopause (GSM) — making leakage and irritation more likely.

    Pelvic floor dysfunction: Pregnancy, vaginal childbirth, and the physical demands of aging can weaken the pelvic floor muscles that support the bladder, uterus, and rectum. Even women who never had children can develop pelvic floor weakness due to chronic constipation, heavy lifting, or connective tissue changes.

    Neurological factors: The bladder is controlled by a network of nerves. Conditions such as diabetes, multiple sclerosis, or even chronic back problems can disrupt these nerve signals, leading to overactive or underactive bladder function.

    Lifestyle and dietary factors: Research from the NIH National Institute of Diabetes and Digestive and Kidney Diseases identifies caffeine, alcohol, carbonated beverages, and artificial sweeteners as common bladder irritants. Excess body weight also increases pressure on the bladder, raising the risk of stress incontinence — with studies showing that a body mass index (BMI) over 30 is associated with a twofold increase in incontinence risk.

    Structural changes: Pelvic organ prolapse — when the bladder, uterus, or rectum shifts from its normal position — is more common after menopause and can cause or worsen bladder symptoms. The CDC estimates that pelvic organ prolapse will affect one in four women over 50 during their lifetime.

    Diagnosis: What to Expect at the Doctor’s Office

    Many women avoid discussing bladder symptoms because they feel embarrassed or assume nothing can be done. The reality is that bladder dysfunction is highly treatable once properly diagnosed — and your physician needs your honest history to help you.

    When you visit your doctor with bladder concerns, you can generally expect:

    • A detailed medical history: Your doctor will ask about symptom frequency, severity, fluid intake, past pregnancies, and any medications you take. Some medications — including diuretics, antihistamines, and antidepressants — can affect bladder function.
    • A bladder diary: You may be asked to track fluid intake, urination frequency, and leakage episodes over a 3-day period. This is one of the most useful diagnostic tools in urology.
    • Physical examination: A pelvic exam can identify signs of atrophy, prolapse, or pelvic floor weakness.
    • Urinalysis: A urine test rules out infection, blood, or glucose in the urine.
    • Urodynamic testing: In some cases, your doctor may refer you for urodynamic studies, which measure how well the bladder stores and releases urine.
    • Cystoscopy: If blood in the urine or structural concerns are identified, a urologist may use a thin camera to examine the bladder interior.

    Most physicians will screen for overactive bladder and incontinence during annual wellness visits. If your doctor hasn’t raised the topic, it’s perfectly appropriate — and encouraged — for you to bring it up yourself.

    Treatment Options: From Lifestyle to Medical Interventions

    The good news is that most bladder conditions in women over 40 respond well to treatment. Clinical evidence supports a stepwise approach — starting with behavioral and lifestyle changes, and progressing to medications or procedures if needed.

    Pelvic floor physical therapy: This is often the first-line recommendation from urologists and gynecologists. A trained pelvic floor therapist teaches you exercises — including Kegel exercises — to strengthen and coordinate the muscles that control bladder function. A 2019 Cochrane Review found that pelvic floor muscle training reduced incontinence episodes by up to 70 percent in women who completed a structured program. This is not something you have to figure out on your own — a referral to a pelvic PT can make a significant difference.

    Bladder training: This behavioral technique involves gradually extending the time between bathroom visits to retrain your bladder to hold more urine. Research from the National Association for Continence suggests that bladder training combined with pelvic floor exercises can be as effective as medication for overactive bladder in some women.

    Dietary modifications: Reducing or eliminating bladder irritants — caffeine, alcohol, spicy foods, acidic fruits, and carbonated drinks — can significantly reduce urgency and frequency. Clinical evidence from Mayo Clinic also supports maintaining adequate hydration (not restricting fluids, which can concentrate urine and worsen irritation).

    Topical estrogen therapy: For women in perimenopause or menopause, local (topical) estrogen applied to the vagina and urethra can restore tissue integrity and significantly reduce urgency, frequency, and recurrent infections. Unlike systemic hormone therapy, topical estrogen has minimal absorption and is considered safe for most women, including many with a history of breast cancer (though always discuss with your doctor).

    Medications: Several FDA-approved medications treat overactive bladder, including anticholinergic drugs and beta-3 adrenergic agonists. Your physician will help determine whether medication is appropriate based on your overall health profile and any other conditions or medications you take.

    Minimally invasive procedures: For women who don’t respond to conservative treatments, options such as Botox injections into the bladder muscle, sacral nerve stimulation (a pacemaker-like device for the bladder), or percutaneous tibial nerve stimulation (PTNS) offer effective alternatives with strong clinical evidence supporting their use.

    Surgical options: For stress incontinence related to pelvic floor prolapse, a mid-urethral sling procedure or prolapse repair may be recommended. These are typically outpatient or same-day surgeries with high success rates.

    If you’re also navigating broader hormonal changes, you may find our article on Vaginal Health After 40 helpful, as it covers related tissue changes that often accompany bladder issues during the menopausal transition.

    Living With Bladder Changes: Practical Day-to-Day Management

    Managing bladder health isn’t just about medical appointments. Daily habits make a meaningful difference in how you feel and function.

    Hydration matters more than you think: Paradoxically, restricting fluids often worsens bladder symptoms. Concentrated urine is a bladder irritant. Aim for adequate daily hydration — roughly 6 to 8 cups of water — while reducing fluids 2 hours before bedtime to limit nocturia.

    Maintain a healthy weight: Even modest weight loss — 5 to 10 percent of body weight — has been shown in clinical trials to significantly reduce stress incontinence episodes in overweight women. A study published in the New England Journal of Medicine found that women who lost an average of 17 pounds experienced a 47 percent reduction in incontinence episodes.

    Bowel health is bladder health: Chronic constipation increases pelvic pressure and worsens bladder symptoms. A high-fiber diet, adequate hydration, and regular physical activity can help keep bowel movements regular and relieve strain on the bladder. For deeper insight into gut function and its connection to pelvic health, see our guide on Celiac Disease and Gut Health.

    Practice timed voiding: Rather than urinating at the first hint of urgency, practice waiting a few minutes longer each time to gradually increase your bladder’s capacity and tolerance.

    Protective products — use them without shame: Absorbent liners and bladder pads are a practical bridge while you pursue treatment. Using them doesn’t mean giving up — it means maintaining your quality of life while you work toward long-term improvement.

    When to Call Your Doctor: Emergency Signs and What to Report

    While most bladder symptoms can be addressed in a routine appointment, some signs require prompt — or even immediate — medical attention.

    Contact your doctor promptly if you notice:

    • Blood in your urine, even once — this is never normal and requires evaluation
    • Sudden onset of incontinence with no prior history
    • Severe pain in the lower abdomen, pelvis, or back alongside urinary symptoms
    • Fever, chills, or nausea along with urinary symptoms (possible kidney infection)
    • Complete inability to urinate (urinary retention) — seek emergency care immediately
    • Recurrent UTIs (three or more in a year) — this warrants investigation for underlying causes

    At your next routine visit, bring up:

    • Any changes in urination frequency, urgency, or control in the past year
    • Episodes of leakage, even minor ones
    • Sleep disruption from nighttime urination
    • Any pelvic pressure, heaviness, or sensation that something is "falling out"

    Your primary care provider or gynecologist can manage many bladder conditions directly, or refer you to a urogynecologist — a specialist in female pelvic medicine — for more complex cases.

    Frequently Asked Questions

    Is urinary leakage a normal part of aging for women?
    Leakage is common, but it is not inevitable or untreatable. Clinical evidence strongly supports that most types of incontinence improve significantly with appropriate treatment. Normalizing leakage as "just aging" is one reason so many women never seek help — and miss out on effective interventions.

    Can drinking more water actually help my bladder?
    Yes — staying well hydrated helps dilute urine, reducing bladder irritation. Restricting fluids in an attempt to urinate less often tends to backfire by concentrating urine, which can worsen urgency and increase UTI risk. The key is to time most of your fluid intake earlier in the day.

    How do I know if I have overactive bladder or a UTI?
    Both conditions can cause urgency and frequency, which is why a urinalysis is an important first step. UTIs typically also cause burning or pain with urination and may produce cloudy or strong-smelling urine. Overactive bladder symptoms tend to be chronic and not associated with infection. Your doctor can distinguish between the two with a simple urine test.

    Are Kegel exercises enough to treat incontinence?
    Kegel exercises — contractions of the pelvic floor muscles — are a foundational tool, but they work best when performed correctly and consistently, and ideally guided by a pelvic floor physical therapist. Many women perform Kegels incorrectly, which limits their benefit. Research suggests that therapist-guided pelvic floor training produces far better outcomes than self-directed exercises alone.

    Is hormone therapy safe for bladder symptoms?
    Local (vaginal/topical) estrogen is widely considered safe and effective for bladder and urethral symptoms related to menopause, including urgency, frequency, and recurrent UTIs. It differs from systemic hormone therapy in that it acts locally with minimal systemic absorption. That said, all hormone decisions should be made in partnership with your physician, who can weigh your individual health history and risk factors.

    Conclusion

    Bladder changes after 40 are real, they are common, and — most importantly — they are treatable. Whether you are experiencing mild urgency, stress leakage, or more disruptive symptoms, you deserve care that restores your comfort, confidence, and freedom.

    The first step is the one most women skip: talking to your doctor. Research consistently shows that women who seek care for bladder symptoms experience meaningful improvement across virtually all treatment approaches. You do not need to restructure your life around a bathroom schedule or quietly accept leakage as your new normal.

    Work with your healthcare provider to identify the right combination of behavioral strategies, physical therapy, and medical treatment for your specific situation. Your bladder health is worth the conversation. For additional context on hormonal health changes that often accompany these symptoms, visit our guide on Ovarian Health After 40.


    This article is for informational and educational purposes only. It does not constitute medical advice, diagnosis, or treatment. Always consult your physician or a qualified healthcare provider before making changes to your health routine or treatment plan.

    Medically reviewed by our editorial health team. Content follows evidence-based standards aligned with CDC and NIH guidelines.

  • Vaginal Health After 40: Changes, Symptoms & Solutions

    Vaginal Health After 40: Changes, Symptoms & Solutions

    What many women mistake for a normal part of aging could actually be a treatable medical condition — and your gynecologist needs to know about it.

    Maria, 52, had been waking up at 3 a.m. for months — not from hot flashes, but from persistent vaginal discomfort that made it hard to sleep, exercise, or feel like herself. She assumed it was just part of getting older and said nothing to her doctor. It wasn’t until a routine visit that her gynecologist identified the problem: genitourinary syndrome of menopause (GSM), a condition affecting up to 50% of postmenopausal women, according to the North American Menopause Society.

    Maria’s story is far from unique. Millions of American women over 40 are silently managing symptoms that affect their daily comfort, intimate relationships, and overall quality of life — and most never bring it up with their healthcare provider.

    This guide covers what happens to vaginal health after 40, why these changes occur, what the clinical evidence says about your treatment options, and when to make that appointment you’ve been putting off.

    What Is Vaginal Health — and Why Does It Change After 40?

    Vaginal health refers to the overall condition of the vagina and surrounding tissues, including the vulva, bladder, and urethra. These tissues are highly responsive to estrogen — the primary female sex hormone — which keeps them thick, lubricated, and elastic.

    Starting in perimenopause (typically the mid-to-late 40s) and continuing through menopause (which the CDC defines as 12 consecutive months without a menstrual period), estrogen levels drop significantly. This hormonal shift directly impacts vaginal tissue in ways that can become progressively more noticeable over time.

    According to the American College of Obstetricians and Gynecologists (ACOG), this condition — formally called genitourinary syndrome of menopause, or GSM — affects approximately 27 to 60% of postmenopausal women. Unlike hot flashes, which often improve over time, GSM symptoms tend to worsen without treatment.

    It is important to understand that vaginal changes after 40 are not inevitable suffering. They are a clinical phenomenon with well-studied, effective treatment options.

    Signs and Symptoms: What You Might Be Noticing

    Symptoms can vary widely from woman to woman. Some experience mild occasional dryness; others deal with chronic discomfort that significantly disrupts daily life. Clinical evidence suggests that the earlier symptoms are addressed, the easier they are to manage.

    Early and common symptoms:

    • Vaginal dryness or a sensation of tightness
    • Decreased natural lubrication, especially during sexual activity
    • Itching, burning, or irritation of the vulva (the outer vaginal area)
    • Mild odor changes without signs of infection
    • Increased sensitivity to soaps, detergents, or clothing
    • More frequent urinary tract infections (UTIs)
    • Mild urinary urgency or leakage

    More advanced or persistent symptoms:

    • Pain during intercourse (dyspareunia) — reported by up to 45% of postmenopausal women, per the NIH
    • Bleeding or spotting after intercourse due to tissue thinning
    • Significant urinary urgency or incontinence
    • Recurrent vaginal infections (bacterial vaginosis or yeast)
    • Pelvic pressure or a feeling of prolapse (when pelvic organs shift downward)

    A 2021 study published in Menopause found that only 7% of women with GSM symptoms reported them to their doctor proactively. The takeaway: if you recognize yourself in this list, you are not alone — and speaking up at your next visit could meaningfully change your comfort and quality of life.

    Causes and Risk Factors

    The primary driver of vaginal changes after 40 is the decline in estrogen production. However, several factors can accelerate or intensify these changes.

    Hormonal causes:

    • Natural menopause (average age of onset in the US: 51, per the NIH)
    • Surgical menopause (removal of the ovaries before natural menopause)
    • Chemotherapy or radiation therapy for cancer, particularly pelvic radiation
    • Hormonal therapies for breast or uterine cancer that suppress estrogen
    • Postpartum breastfeeding (temporary estrogen reduction)

    Lifestyle and behavioral risk factors:

    • Cigarette smoking, which impairs blood flow to vaginal tissue
    • Sedentary lifestyle (reduced circulation affects tissue health)
    • Use of harsh soaps, douches, or scented products that disrupt vaginal pH
    • Infrequent sexual activity, which research suggests may reduce natural lubrication capacity

    Medical and genetic factors:

    • Autoimmune conditions such as Sjögren’s syndrome, which causes widespread dryness
    • Diabetes, which can affect nerve function and tissue health
    • History of vaginal infections that altered the microbiome
    • Certain antihistamines, antidepressants, and blood pressure medications that reduce moisture

    According to the American Diabetes Association, women with Type 2 diabetes are at significantly higher risk for recurrent vaginal infections and urinary issues, making blood sugar management a key component of vaginal health maintenance.

    Diagnosis: What to Expect at Your Appointment

    Many women feel embarrassed discussing vaginal symptoms — but your gynecologist or primary care provider is trained specifically for this. There is no need to minimize what you are experiencing.

    A thorough evaluation typically includes:

    • Medical history review: Your provider will ask about menstrual status, symptoms, medications, sexual activity, and any recent infections.
    • Pelvic exam: A visual and physical exam to assess tissue color, texture, moisture, and any signs of thinning (atrophy), inflammation, or prolapse.
    • Vaginal pH testing: Healthy vaginal pH is typically below 4.5. A pH above 5.0 may suggest atrophy, bacterial vaginosis, or trichomoniasis (a sexually transmitted infection).
    • Vaginal swab or culture: To rule out infection if discharge, odor, or itching is prominent.
    • Pap smear: If due, to screen for cervical changes. ACOG recommends Pap smears every 3 to 5 years for women 21 to 65, depending on age and prior results.
    • Urinalysis: If urinary symptoms are present, to evaluate for UTI or bladder issues.

    In some cases, especially if pelvic organ prolapse or urinary incontinence is suspected, your provider may refer you to a urogynecologist — a specialist in pelvic floor disorders.

    The right time to seek diagnosis is now, not after symptoms become unbearable. Earlier intervention is consistently associated with better outcomes.

    Treatment Options: What the Evidence Says

    Treatment for vaginal health concerns after 40 has advanced significantly. Clinical guidelines from ACOG and the North American Menopause Society support a range of options — from simple over-the-counter products to prescription therapies.

    Non-Hormonal Approaches

    Vaginal moisturizers: Applied regularly (not just during sex), these products help maintain hydration in vaginal tissue. Clinical trials, including a review published in Obstetrics & Gynecology, found that regular use of vaginal moisturizers reduced dryness and discomfort comparably to low-dose estrogen in some women with mild symptoms.

    Lubricants: Water-based or silicone-based lubricants used during sexual activity can significantly reduce friction and discomfort. Avoid petroleum-based products or anything with fragrances, which can irritate sensitive tissue.

    Pelvic floor physical therapy: A growing body of evidence supports pelvic floor physical therapy for improving vaginal tone, reducing pain during intercourse, and addressing urinary leakage. The NIH acknowledges this as an effective, non-pharmaceutical first-line option.

    Hormonal Therapies

    Local vaginal estrogen: Available as creams, rings, or suppositories, low-dose vaginal estrogen is considered one of the most effective treatments for GSM. Because it is applied locally and absorbed minimally into the bloodstream, it is generally considered safe even for women who cannot use systemic hormone therapy. Your physician can determine if this is appropriate for your history.

    Ospemifene (Osphena): An FDA-approved oral non-estrogen medication for moderate to severe dyspareunia (painful intercourse) related to menopause. It acts as a selective estrogen receptor modulator (SERM), meaning it mimics estrogen’s effects in vaginal tissue without acting like estrogen elsewhere.

    Systemic hormone therapy (HT): For women managing multiple menopause symptoms (hot flashes, mood changes, sleep disruption, and vaginal symptoms together), systemic hormone therapy may be considered. The decision is highly individualized and should be made in detailed conversation with your doctor, weighing personal risk factors including history of breast cancer, blood clots, or cardiovascular disease.

    Dehydroepiandrosterone (DHEA) / Prasterone: An FDA-approved intravaginal insert (Intrarosa) that the body converts to estrogen and testosterone locally in vaginal tissue. Research published in the Journal of Sexual Medicine found it improved pain, dryness, and sexual function in postmenopausal women.

    For women interested in the broader hormonal picture, our article on Ovarian Health After 40: Cysts, Hormones & Warning Signs provides helpful context on how ovarian function changes with age.

    Living With These Changes: Daily Habits That Support Vaginal Health

    Beyond medical treatment, several evidence-informed daily practices can meaningfully support vaginal health and comfort as you age.

    • Wear breathable fabrics: Loose-fitting, cotton underwear reduces moisture buildup and lowers infection risk. Avoid tight synthetic materials, especially during exercise.
    • Avoid douching and scented products: The vagina is self-cleaning. Douching disrupts the natural bacterial balance (the vaginal microbiome) and raises infection risk. Plain warm water is sufficient for external cleansing.
    • Stay hydrated: Systemic hydration supports mucous membrane health throughout the body, including vaginal tissue.
    • Maintain sexual activity if comfortable: Regular sexual stimulation — solo or partnered — is associated with better vaginal blood flow and lubrication capacity, according to research from the Mayo Clinic.
    • Quit smoking: Smoking is associated with earlier menopause onset and reduced estrogen circulation, both of which accelerate vaginal tissue changes. The CDC notes that women who smoke reach menopause approximately two years earlier than non-smokers.
    • Manage blood sugar: Women with diabetes should prioritize glucose control, as elevated blood sugar directly affects vaginal tissue health and infection susceptibility.
    • Support bone and overall hormonal health: Hormonal changes that affect the vagina also affect bones. Our guide on Bone Density After 50: How to Protect Your Skeleton explores this connection in detail.

    When to Call Your Doctor — and Emergency Warning Signs

    Most vaginal health concerns after 40 are not emergencies — but some symptoms require prompt medical attention. Knowing the difference is essential.

    Schedule a routine appointment if you notice:

    • Persistent dryness or irritation lasting more than two weeks
    • Pain during intercourse that is new or worsening
    • Unusual discharge (changes in color, consistency, or amount)
    • Increased frequency of UTIs (more than two per year)
    • Urinary leakage that affects daily activities
    • Any new lumps, lesions, or skin changes on the vulva

    Seek care promptly (within 24-48 hours) if you experience:

    • Significant vaginal bleeding after menopause — this always requires evaluation, as it can indicate endometrial (uterine lining) changes or, in rare cases, cancer
    • Severe pain or pressure in the pelvic region
    • Signs of a severe infection: fever, chills, foul-smelling discharge, or extreme swelling
    • Sudden inability to urinate or severe urinary pain

    Call 911 or go to the ER immediately if you have: sudden heavy vaginal bleeding with dizziness, fainting, or rapid heart rate — these may indicate hemorrhage requiring emergency intervention.

    At your next routine visit, consider telling your provider: "I have some vaginal symptoms I’ve been hesitant to mention — I’d like to discuss them today." That single sentence can open a conversation that changes your quality of life.

    Frequently Asked Questions

    Is vaginal dryness after 40 normal, or is it a medical condition?

    It is extremely common, but "common" does not mean you have to accept it. Vaginal dryness related to estrogen decline is a clinical condition called genitourinary syndrome of menopause (GSM), and it responds well to treatment. Normalizing suffering is not the same as it being inevitable.

    Can vaginal health affect urinary health?

    Yes — the vagina, urethra, and bladder all share estrogen-sensitive tissue. As estrogen declines, changes in the vaginal environment often coincide with urinary symptoms like urgency, frequency, leakage, and susceptibility to UTIs. This is why the condition is called genitourinary syndrome, not just vaginal atrophy.

    Is local vaginal estrogen safe if I have a history of breast cancer?

    This is one of the most common and important questions. Clinical guidelines, including those from ACOG and the Society of Gynecologic Oncology, indicate that low-dose vaginal estrogen may be appropriate for some breast cancer survivors — particularly those whose cancer was hormone receptor-negative. However, this decision must be made individually with your oncologist and gynecologist. Non-hormonal options (moisturizers, ospemifene) are also effective alternatives.

    Do probiotics help with vaginal health?

    Research suggests that certain probiotic strains — particularly Lactobacillus species — may help maintain healthy vaginal pH and microbiome balance. While the evidence is still emerging, clinical studies indicate potential benefit, especially for women prone to recurrent bacterial vaginosis. Always discuss supplement use with your provider before starting.

    At what age do these changes typically begin?

    Many women begin noticing subtle changes in their late 40s during perimenopause, even before periods stop entirely. According to the NIH, estrogen begins declining gradually in the mid-40s, and vaginal tissue changes can begin years before official menopause. Early recognition means earlier, easier management.

    Conclusion

    Vaginal health after 40 is a legitimate, medically recognized area of women’s health — and one that deserves the same open conversation as any other chronic symptom. Whether you’re experiencing mild dryness or more disruptive symptoms that affect your intimacy, comfort, or daily activity, you have real options backed by solid clinical evidence.

    The most important step is the one many women delay: telling your doctor. Your symptoms are not too embarrassing, too minor, or "just part of aging." They are data — and your healthcare provider needs that data to help you feel your best in this chapter of life.

    You deserve comfort, confidence, and care at every age. Start that conversation at your next visit.

    This article is for informational and educational purposes only. It does not constitute medical advice, diagnosis, or treatment. Always consult your physician or a qualified healthcare provider before making changes to your health routine or treatment plan.

    Medically reviewed by our editorial health team. Content follows evidence-based standards aligned with CDC and NIH guidelines.
  • Ovarian Health After 40: Cysts, Hormones & Warning Signs

    Ovarian Health After 40: Cysts, Hormones & Warning Signs

    Your ovaries do far more than produce eggs — and after 40, the changes they undergo can affect your energy, mood, weight, and long-term disease risk in ways most women never expect.

    When Linda, 44, felt a dull ache in her lower abdomen that came and went for weeks, she assumed it was just stress or a pulled muscle. It wasn’t until a routine pelvic ultrasound that her gynecologist found a small ovarian cyst — benign, as it turned out, but a wake-up call that her ovarian health deserved more attention than she had ever given it.

    Linda’s experience is far from unusual. According to the American College of Obstetricians and Gynecologists (ACOG), most women will develop at least one ovarian cyst during their lifetime, and the risk of ovarian conditions — including cysts, diminished reserve, and hormonal shifts — increases significantly as women enter their 40s. Yet ovarian health is one of the most underdiscussed topics in women’s preventive care.

    In this guide, you’ll learn what your ovaries are doing after 40, what symptoms deserve medical attention, how ovarian cysts are diagnosed and managed, and — critically — what warning signs should never be ignored.

    What Is Ovarian Health, and Why Does It Change After 40?

    Your ovaries are two small, almond-shaped organs located on either side of your uterus. They serve two primary functions: releasing eggs (ovulation) and producing the hormones estrogen and progesterone that regulate your menstrual cycle, bone density, cardiovascular health, mood, and metabolism.

    After 40, both of these functions begin to shift. You’re entering what clinicians call the perimenopausal transition — a gradual process that can begin anywhere from your late 30s to mid-40s, long before your periods actually stop. During this time, your ovaries produce follicles (fluid-filled sacs that contain eggs) less predictably, estrogen levels fluctuate widely, and ovulation may become irregular.

    The National Institute on Aging (NIA) notes that the average age of menopause in the US is 51, meaning women typically spend a decade or more in perimenopause. During these years, ovarian function doesn’t simply decline in a straight line — it becomes erratic, which is exactly why symptoms in this phase can feel confusing and unpredictable.

    Understanding what’s normal during this transition, and what’s not, is essential to protecting your long-term health.

    Common Ovarian Conditions After 40

    Several ovarian conditions become more or less relevant depending on where you are in your reproductive journey. Here’s what clinical evidence indicates you should know:

    Ovarian Cysts

    A cyst is a fluid-filled sac that forms on or inside an ovary. Most are functional cysts — meaning they develop as part of a normal menstrual cycle, typically when a follicle doesn’t release its egg or doesn’t dissolve after releasing it. These cysts are extremely common and usually resolve on their own within a few weeks to months.

    However, other types of cysts can develop regardless of your cycle:

    • Dermoid cysts: Contain tissue like hair or skin; generally benign but may require removal
    • Cystadenomas: Develop from ovarian tissue and can grow large
    • Endometriomas: Linked to endometriosis, these cysts contain old menstrual blood
    • Hemorrhagic cysts: Form when a cyst bleeds into itself

    According to the NIH’s National Library of Medicine, the vast majority of ovarian cysts in premenopausal women are benign. However, after menopause, any new cyst warrants closer evaluation because the baseline risk profile changes.

    Diminished Ovarian Reserve (DOR)

    Diminished ovarian reserve refers to a reduction in the number and quality of eggs remaining in the ovaries. While this is primarily a concern for fertility, it also signals hormonal shifts that can affect bone health, cardiovascular function, and mood. Research suggests women with premature ovarian insufficiency (POI) — where ovarian function declines before age 40 — face a higher risk of osteoporosis and cardiovascular disease if left unmanaged.

    Ovarian Torsion

    This is a less common but serious condition in which an ovary twists around its supporting ligaments, cutting off its blood supply. Ovarian torsion is a medical emergency. It can be associated with cysts or other ovarian enlargements and requires immediate surgical intervention.

    Signs and Symptoms to Know

    Ovarian conditions are notoriously quiet in their early stages — a key reason why regular gynecological care is so important. That said, clinical evidence indicates several symptoms that may signal an ovarian issue worth discussing with your doctor.

    Common symptoms associated with ovarian cysts:

    • Dull, aching pelvic pain — especially on one side
    • A sense of fullness, bloating, or pressure in the lower abdomen
    • Pain during intercourse (dyspareunia)
    • Irregular menstrual cycles or changes in flow
    • Frequent urge to urinate if the cyst presses on the bladder
    • Difficulty emptying the bowel if the cyst presses on the rectum

    Symptoms that may indicate hormonal changes from shifting ovarian function:

    • Irregular or missed periods
    • Hot flashes and night sweats
    • Mood swings, irritability, or low mood
    • Fatigue and sleep disruption
    • Brain fog or difficulty concentrating
    • Reduced libido
    • Vaginal dryness

    A 2023 study published in the journal Menopause found that more than 70% of women in perimenopause report at least four concurrent symptoms — yet fewer than half report discussing all of them with their physician. If any of these symptoms are affecting your quality of life, they deserve a full clinical conversation.

    If you’re also experiencing thyroid-related symptoms, it’s worth reading our guide on Thyroid Health After 50: Signs, Causes & Treatment, since hypothyroidism and ovarian hormonal changes often overlap symptomatically in women over 40.

    Causes and Risk Factors

    Understanding why ovarian conditions develop helps you identify where you may have some control — and where you don’t.

    Genetic and biological factors:

    • Family history: A family history of ovarian cysts, polycystic ovary syndrome (PCOS), or ovarian cancer increases your personal risk
    • Age: The perimenopausal transition itself is a primary driver of ovarian changes after 40
    • Previous ovarian conditions: Women with a history of cysts are more likely to develop them again
    • Endometriosis: Increases the likelihood of endometriomas

    Lifestyle and hormonal factors:

    • Hormonal imbalances: Conditions that disrupt normal hormonal cycling increase cyst formation risk
    • Obesity: Excess body fat, particularly abdominal fat, is associated with increased estrogen production and hormonal disruption; the CDC reports that 41.9% of US adults are obese, a factor with documented implications for gynecological health
    • Smoking: Research suggests smoking is linked to higher rates of ovarian dysfunction and earlier menopause onset
    • Fertility treatments: Ovarian stimulation drugs can increase the risk of multiple cyst formation (ovarian hyperstimulation syndrome)

    Ovarian cancer risk context: The American Cancer Society (ACS) estimates that approximately 19,680 new cases of ovarian cancer will be diagnosed annually in the US. While most ovarian cysts are benign, it’s important to note that ovarian cancer is the fifth leading cause of cancer-related death among US women — underscoring why monitoring and early evaluation matter.

    Diagnosis: What to Expect

    If your doctor suspects an ovarian condition, the diagnostic process is typically straightforward and non-invasive in its initial steps.

    Pelvic Exam: Your gynecologist will first perform a bimanual pelvic exam to check for any unusual enlargement or tenderness in the ovarian area. This is often the first step and is part of a routine annual gynecological visit.

    Transvaginal Ultrasound: This is the most effective imaging tool for evaluating ovarian cysts and other structural changes. A small ultrasound probe is inserted into the vagina to produce detailed images of the ovaries and uterus. It can identify the size, location, and composition (fluid-filled vs. solid) of any cyst.

    Blood Tests: Your doctor may order:

    • CA-125: A tumor marker that, when elevated, may suggest the need for further investigation — though it can also be elevated in non-cancerous conditions like endometriosis
    • Hormone panels: Including FSH (follicle-stimulating hormone), LH, estradiol, and AMH (anti-Müllerian hormone) to assess ovarian reserve and menopausal status
    • Complete blood count (CBC): If infection or hemorrhage is suspected

    CT Scan or MRI: Used in more complex cases to provide additional detail, especially if malignancy needs to be ruled out.

    Most physicians recommend that women over 40 get a pelvic exam at every annual wellness visit. If you’re experiencing symptoms, don’t wait — request an evaluation at your earliest convenience.

    Treatment Options

    Treatment depends entirely on the type, size, and characteristics of the ovarian condition — as well as your age, menopausal status, and overall health. Most clinical guidelines emphasize individualized care.

    Watchful Waiting

    For small, simple, fluid-filled cysts in premenopausal women, most physicians recommend a period of observation. Clinical evidence from the Mayo Clinic suggests that the majority of these cysts resolve within two to three menstrual cycles without intervention. A follow-up ultrasound in 6 to 12 weeks is typically scheduled to confirm resolution.

    Hormonal Contraceptives

    Oral contraceptives or hormonal IUDs are sometimes prescribed to help regulate hormonal cycling and reduce the likelihood of new functional cysts forming. They do not shrink existing cysts but may prevent recurrence in women who develop them frequently.

    Surgical Intervention

    Surgery is recommended when a cyst:

    • Is large (generally over 5–10 cm depending on type)
    • Is growing over time
    • Has complex features (solid components, irregular borders)
    • Is causing severe symptoms or has twisted (torsion)
    • Occurs in a postmenopausal woman and raises concern for malignancy

    Most cyst removals are performed via laparoscopy — a minimally invasive procedure using small incisions and a camera — with a relatively quick recovery time. In some cases, especially when malignancy is a concern, an oophorectomy (removal of one or both ovaries) may be recommended.

    Hormonal Support for Ovarian Decline

    For women experiencing perimenopausal symptoms related to declining ovarian function, hormone therapy (HT) may be an option. The Menopause Society (formerly NAMS) supports individualized HT use in appropriate candidates — particularly those under 60 or within 10 years of menopause onset — as effective for managing hot flashes, protecting bone density, and improving quality of life. Discuss your personal risk profile thoroughly with your physician.

    Lifestyle Modifications as Complement

    While lifestyle changes don’t treat existing cysts, research suggests they support overall hormonal balance and reduce inflammation:

    • Anti-inflammatory diet: Rich in vegetables, whole grains, lean protein, and omega-3 fatty acids
    • Regular physical activity: At least 150 minutes of moderate exercise weekly per CDC guidelines supports hormonal regulation and weight management
    • Stress reduction: Chronic stress elevates cortisol, which can disrupt sex hormone balance
    • Adequate sleep: Hormonal regulation is closely tied to sleep quality — a relationship well-documented in reproductive health research

    For further reading on how hormonal health intersects with stress and sleep, our guide on Cervical Health: HPV, Pap Smears & Prevention Guide offers complementary insights on women’s reproductive wellness visits.

    Living With Ovarian Changes: Daily Management and Prevention

    Living with ovarian cysts or navigating the hormonal shifts of perimenopause doesn’t have to feel overwhelming. Most women move through this phase with informed support and a proactive relationship with their healthcare provider.

    Practical strategies that clinical evidence supports:

    • Keep all follow-up imaging appointments. If a cyst is being monitored, skipping ultrasounds removes the safety net that catches any concerning changes early.
    • Track your symptoms. A simple symptom journal — noting pain location, menstrual changes, bloating, or mood shifts — gives your doctor concrete data to work with.
    • Prioritize bone health. As ovarian estrogen production declines, bone density can drop. Clinical guidelines from the National Osteoporosis Foundation recommend adequate calcium and vitamin D intake, along with weight-bearing exercise.
    • Protect your cardiovascular health. Estrogen has a protective effect on the heart; as levels decline, cardiovascular risk rises. The American Heart Association recommends that women entering perimenopause discuss heart health proactively with their physician.
    • Don’t self-diagnose from online searches. Ovarian symptoms overlap with many other conditions, including digestive issues and musculoskeletal pain. Only clinical evaluation can determine the true cause.

    Understanding the broader picture of your hormonal health after 40 also means paying attention to how gut health, mood, and metabolism intersect. Our article on The Gut-Brain Connection: How Your Digestive Health Affects Your Mind explores how these systems interact in ways that are especially relevant during hormonal transitions.

    When to Call Your Doctor — and Emergency Red Flags

    Knowing when a symptom is routine versus urgent can genuinely save your life. Here’s how to distinguish the two:

    Schedule a medical appointment (non-emergency) if you experience:

    • Persistent pelvic pain lasting more than a few days
    • Bloating that doesn’t improve with dietary changes over several weeks
    • Changes in your menstrual cycle that are new or unexplained
    • Pain during sex that is new or worsening
    • A feeling of pressure or fullness in your pelvis
    • Unexpected weight gain or difficulty losing weight despite no lifestyle changes

    Seek emergency care immediately if you experience:

    • Sudden, severe pelvic or abdominal pain — this may indicate ovarian torsion or a ruptured cyst
    • Pain accompanied by fever and vomiting
    • Signs of shock: dizziness, lightheadedness, rapid heartbeat, fainting
    • Vaginal bleeding that is unusually heavy or occurs after menopause

    Ovarian torsion and ruptured hemorrhagic cysts are medical emergencies that require immediate surgical care. Do not wait to see if the pain resolves on its own if it is sudden and severe.

    Frequently Asked Questions

    Q: Can ovarian cysts cause weight gain?
    A: Large cysts can cause abdominal bloating that may feel like weight gain, but they rarely cause actual fat accumulation. Hormonal shifts associated with perimenopausal ovarian changes — particularly declining estrogen — can contribute to metabolic changes that make weight management more difficult. This varies from person to person and is worth discussing with your doctor.

    Q: Should I be worried about ovarian cancer if I have a cyst?
    A: Most ovarian cysts are benign, especially in premenopausal women. However, the ACS recommends that any new cyst in a postmenopausal woman be evaluated carefully. Your doctor will use ultrasound characteristics and blood markers (like CA-125) to assess risk. A cyst diagnosis is not a cancer diagnosis.

    Q: How do I know if my symptoms are from ovarian issues or just perimenopause?
    A: The honest answer is that you often can’t tell without clinical evaluation. Many ovarian symptoms — bloating, pelvic pressure, irregular periods — overlap with perimenopausal changes. A pelvic exam, hormone panel, and ultrasound can help your doctor distinguish between the two. Don’t try to self-diagnose.

    Q: Is it safe to exercise if I have an ovarian cyst?
    A: For most small, uncomplicated cysts, light to moderate exercise is considered safe. However, high-impact activities or intense core work may worsen discomfort. Most physicians recommend avoiding vigorous exercise until you’ve had a clinical evaluation and know the size and type of cyst. Always follow your doctor’s individualized guidance.

    Q: Can diet reduce the risk of ovarian cysts?
    A: No specific diet has been proven to prevent ovarian cysts. However, research suggests that an anti-inflammatory diet rich in fiber, healthy fats, and lean protein supports hormonal balance and reduces systemic inflammation — factors that may influence overall reproductive health. A registered dietitian can help you build a plan appropriate for your needs.

    Moving Forward With Confidence

    Ovarian health after 40 is a dynamic, evolving landscape — one that deserves the same attention you give to your heart, bones, and blood pressure. Whether you’re navigating an incidental cyst finding, managing perimenopausal symptoms, or simply trying to stay ahead of your preventive care, knowledge is your most powerful tool.

    The research is clear: women who maintain regular gynecological care, communicate openly with their physicians, and address new symptoms early have better outcomes across every major ovarian condition. This isn’t about fear — it’s about being an informed, empowered participant in your own health. Talk to your doctor, ask the hard questions, and never dismiss symptoms that feel persistent or new.

    Your ovaries have served you well. Now it’s time to return the favor.


    Medical Disclaimer: This article is for informational and educational purposes only. It does not constitute medical advice, diagnosis, or treatment. Always consult your physician or a qualified healthcare provider before making changes to your health routine or treatment plan.

    Medically reviewed by our editorial health team. Content follows evidence-based standards aligned with CDC and NIH guidelines.

  • Breast Health After 40: Screenings, Changes & Risk Reduction

    Breast Health After 40: Screenings, Changes & Risk Reduction

    Most breast cancers are found in women over 40 — yet millions still skip their annual mammogram or dismiss warning signs as normal aging.

    Why Breast Health Deserves Your Full Attention After 40

    Linda, 44, noticed a small lump during a routine self-exam. She almost dismissed it — she had dense breast tissue, and her doctor had mentioned lumps could be benign. But she made the appointment anyway. That decision led to an early-stage diagnosis, successful treatment, and years of healthy living ahead.

    According to the American Cancer Society, breast cancer is the most commonly diagnosed cancer in American women, with approximately 310,720 new invasive breast cancer cases expected in 2024. It is also the second leading cause of cancer death in women in the United States.

    The good news: when caught early, the five-year survival rate for localized breast cancer exceeds 99%, according to the National Cancer Institute. That makes proactive breast health — understanding what is normal, what is not, and when to get screened — one of the most powerful things you can do for yourself after 40.

    This guide covers what changes to expect in your breasts as you age, what symptoms deserve medical attention, how screenings work, and evidence-based steps you can take to reduce your risk.

    What Happens to Breast Tissue After 40?

    Breast tissue is not static. It changes throughout your entire life, influenced by hormonal shifts, weight fluctuations, pregnancy, breastfeeding, and aging. Understanding these changes helps you recognize what is normal versus what warrants a call to your doctor.

    During your 40s and into perimenopause, estrogen levels begin to fluctuate. This hormonal shift causes glandular tissue (the milk-producing structures) to gradually replace with fatty tissue. For many women, this actually makes mammograms easier to read — but dense breast tissue can persist and is itself considered a risk factor for breast cancer.

    Common normal changes you may notice after 40 include:

    • Breasts feeling less firm or full
    • Temporary tenderness or swelling tied to your menstrual cycle
    • Slight size asymmetry (common in most women)
    • Noncancerous cysts that come and go with your cycle
    • Nipple changes related to hormonal shifts

    According to Johns Hopkins Medicine, most breast lumps — up to 80% — are benign. But any new lump, thickening, or persistent change should be evaluated by a healthcare provider. This varies from person to person, and only a clinical exam or imaging can determine what is happening in your specific case.

    Signs and Symptoms: What to Watch For

    Knowing your body’s baseline is the foundation of breast health. The more familiar you are with what is normal for you, the sooner you can recognize something that does not belong.

    Early or subtle signs to bring to your doctor’s attention:

    • A new lump or thickening in the breast or underarm area
    • Changes in breast size or shape that are unexplained
    • Skin dimpling, puckering, or a texture resembling an orange peel
    • Nipple inversion (turning inward) when this is new
    • Nipple discharge that is clear, bloody, or occurs without squeezing
    • Persistent breast pain in one specific area (not tied to your cycle)
    • Redness, scaling, or thickening of the nipple or breast skin

    Signs that require prompt medical evaluation:

    • A rapidly growing lump or mass
    • Bloody nipple discharge from one breast
    • Swelling in the entire breast, especially with redness and warmth (could indicate inflammatory breast cancer, a rare but aggressive form)
    • Skin changes that resemble a rash or look like bruising that does not resolve

    A 2022 analysis published through the NIH’s PubMed database found that women who performed regular breast self-awareness — not necessarily formal self-exams, but being attentive to changes — were more likely to present with earlier-stage diagnoses.

    Causes and Risk Factors: What Raises Your Odds

    Breast cancer does not have a single cause. Research suggests it results from a combination of genetic, hormonal, reproductive, and lifestyle factors. Understanding your personal risk profile helps you and your doctor make smarter screening and prevention decisions.

    Factors you cannot change:

    • Age: Risk increases significantly after 40. The CDC reports that most breast cancers are diagnosed in women aged 50 and older.
    • Gender: Women are about 100 times more likely than men to develop breast cancer.
    • Family history: Having a first-degree relative (mother, sister, daughter) with breast cancer roughly doubles your risk.
    • Genetic mutations: BRCA1 and BRCA2 gene mutations significantly increase lifetime risk. Other genes such as PALB2 and ATM also play a role.
    • Dense breast tissue: Women with dense breasts have both a higher risk of breast cancer and a greater chance that cancer can be hidden on a mammogram.
    • Early menstruation or late menopause: Longer lifetime exposure to estrogen increases risk.

    Factors influenced by lifestyle and environment:

    • Alcohol consumption (research consistently links regular drinking to increased risk)
    • Obesity or significant weight gain after menopause
    • Physical inactivity
    • Postmenopausal hormone therapy (specifically combined estrogen-progestin therapy used long-term)
    • Having a first child after age 30 or never having children
    • Not breastfeeding

    It is important to note that having one or more risk factors does not mean you will develop breast cancer. Conversely, most women who develop it have no significant known risk factors beyond age and gender.

    Diagnosis: Screenings and What to Expect

    Screening is where early detection begins. The goal of breast cancer screening is to find cancer before it causes symptoms — when it is most treatable. Here is what clinical evidence and major US health organizations recommend.

    Mammography remains the gold standard for routine breast cancer screening. The American Cancer Society recommends that women at average risk begin annual mammograms at age 45, though women aged 40-44 have the option to start. Women 55 and older can transition to every two years or continue annually based on personal preference and physician guidance.

    3D Mammography (Tomosynthesis) is now widely available and offers a clearer, layer-by-layer image of breast tissue. Clinical evidence indicates it finds more cancers and results in fewer callbacks for additional imaging compared to standard 2D mammograms.

    Breast MRI is recommended alongside mammography for women at high risk (generally defined as a 20% or greater lifetime risk), including those with BRCA mutations or a significant family history.

    Ultrasound may be used alongside mammography in women with dense breast tissue to improve detection accuracy.

    If you have not already, talk to your doctor about your individual risk level. Your physician may recommend a formal risk assessment tool such as the Tyrer-Cuzick model to calculate your lifetime risk and tailor your screening schedule accordingly. You may also want to review our guide on cervical health and preventive screenings as part of a broader approach to women’s health monitoring.

    Treatment Options: What Modern Medicine Offers

    If a suspicious finding leads to a biopsy and a breast cancer diagnosis, treatment options have advanced significantly. Most physicians individualize treatment plans based on the cancer’s type, stage, and molecular profile, as well as the patient’s overall health and personal preferences.

    Surgery: Options range from lumpectomy (removing only the tumor and some surrounding tissue) to mastectomy (removing one or both breasts). Clinical evidence shows that for early-stage breast cancer, lumpectomy followed by radiation is equally effective as mastectomy in terms of survival rates.

    Radiation therapy is commonly used after lumpectomy to destroy any remaining cancer cells in the breast.

    Chemotherapy uses drugs to kill cancer cells and may be given before surgery (neoadjuvant) to shrink tumors or after (adjuvant) to reduce recurrence risk.

    Hormone therapy (such as tamoxifen or aromatase inhibitors) is used for hormone receptor-positive breast cancers, which represent about 70-80% of all cases. These treatments block estrogen from fueling cancer cell growth.

    Targeted therapy and immunotherapy have expanded options significantly, especially for HER2-positive and triple-negative breast cancers. Drugs like trastuzumab (Herceptin) specifically target proteins on cancer cells, sparing healthy tissue.

    Lifestyle modifications — including maintaining a healthy weight, limiting alcohol, and staying physically active — are recommended as important complements to medical treatment, not replacements. The American Cancer Society notes that regular exercise during and after treatment can improve outcomes and quality of life.

    Reducing Your Risk: Prevention Strategies Backed by Evidence

    You cannot eliminate your risk entirely, but research suggests that several lifestyle choices can meaningfully reduce it — particularly for women in their 40s, 50s, and 60s who still have decades of health ahead.

    Maintain a healthy weight after menopause. A large meta-analysis cited by the NIH found that postmenopausal women who were obese had a 20-40% higher risk of breast cancer compared to women at a healthy weight. This is largely because fat tissue produces estrogen, which can fuel hormone-sensitive breast cancer cells.

    Limit or avoid alcohol. Even one drink per day has been associated with a modest but measurable increase in breast cancer risk. The American Cancer Society reports that women who consume two to three alcoholic drinks daily have about a 20% higher risk than non-drinkers.

    Exercise regularly. Clinical evidence consistently links physical activity to reduced breast cancer risk. Most physicians recommend at least 150 minutes of moderate-intensity aerobic activity per week — such as brisk walking, swimming, or cycling.

    Limit postmenopausal hormone therapy. If you are using combined hormone therapy for menopause symptoms, discuss the risks and benefits with your doctor. Using the lowest effective dose for the shortest necessary duration is the approach most physicians recommend.

    Breastfeed if possible. Research suggests breastfeeding for at least a year reduces lifetime risk, possibly due to hormonal effects that delay ovulation.

    Consider chemoprevention if you are high-risk. For women with a significantly elevated risk, medications such as tamoxifen, raloxifene, or aromatase inhibitors may reduce risk by 30-50%, according to the NIH. This is a conversation worth having with your physician or a breast health specialist. Hormonal changes also intersect with broader health concerns — our article on menopause and heart health explores how estrogen shifts affect cardiovascular risk, which often goes hand-in-hand with breast cancer prevention discussions.

    When to Call Your Doctor or Seek Emergency Care

    Breast health is not just about annual screenings. Knowing when to pick up the phone between appointments is just as important.

    Call your doctor within the next few days if you notice:

    • A new lump or thickening that persists through one full menstrual cycle
    • Any nipple discharge not related to breastfeeding
    • Skin changes on the breast or nipple that do not resolve
    • Unexplained changes in breast shape or contour

    Seek prompt medical attention (same day) if you experience:

    • A rapidly growing lump that appears over days
    • Bloody discharge from a nipple
    • A breast that appears red, warm, swollen, and inflamed without an infection history — this could indicate inflammatory breast cancer, which can progress quickly
    • Swollen lymph nodes under your arm that are new and persistent

    At your next scheduled visit, bring a list of any changes you have noticed — even if you are not sure they matter. Tell your doctor your family history, any medications or supplements you are taking, and whether you have had prior biopsies or imaging. This context helps your physician make the most informed decisions about your care. You might also discuss thyroid health at this visit, since thyroid conditions and hormonal changes often overlap in women over 40 — see our overview of thyroid health after 50 for more background.

    Frequently Asked Questions About Breast Health After 40

    Q: At what age should I start getting mammograms?
    A: The American Cancer Society recommends that women at average risk have the option to begin annual mammograms at age 40, with a strong recommendation to start by age 45. However, your physician may suggest starting earlier if you have a family history of breast cancer or known genetic risk factors. Always discuss your personal timeline with your doctor.

    Q: I have dense breasts. Does that change my screening plan?
    A: Yes, it can. Dense breast tissue makes mammograms harder to read and is independently associated with a higher breast cancer risk. Many states have passed laws requiring radiologists to notify patients about breast density. If you have dense breasts, your doctor may recommend supplemental screening with ultrasound or MRI in addition to your annual mammogram.

    Q: Can I rely on self-exams alone to detect breast cancer?
    A: Self-awareness is valuable, but self-exams alone are not a substitute for clinical screenings. Many tumors are too small to feel during early stages and can only be detected on imaging. Most physicians recommend staying familiar with your breasts so you can report changes promptly, while still keeping up with scheduled mammograms and clinical exams.

    Q: Is breast pain a sign of cancer?
    A: Breast pain (mastalgia) is extremely common and is most often related to hormonal fluctuations, caffeine sensitivity, ill-fitting bras, or benign cysts — not cancer. Research suggests that pain alone is rarely the first symptom of breast cancer. That said, if you have persistent, localized pain that does not vary with your cycle, bring it to your doctor’s attention.

    Q: How does menopause affect my breast cancer risk?
    A: After menopause, your risk of breast cancer actually increases with age, even as estrogen from your ovaries decreases. The greater the cumulative lifetime exposure to estrogen — from early periods, late menopause, or postmenopausal hormone therapy — the higher the risk. Maintaining a healthy weight after menopause is one of the most effective modifiable steps, because fat tissue continues producing estrogen after the ovaries stop.

    Moving Forward With Confidence and Awareness

    Breast health after 40 is not about fear — it is about being informed, proactive, and empowered. The science is clear: early detection saves lives, lifestyle choices matter, and open communication with your healthcare provider is irreplaceable.

    Stay current with your screening schedule. Know your body well enough to recognize when something feels different. Ask your doctor about your personal risk level and what screening tools are right for you. And remember — no article, however thorough, replaces a conversation with a qualified physician who knows your complete health history.

    You have every reason to be proactive about your breast health today.


    Medical Disclaimer: This article is for informational and educational purposes only. It does not constitute medical advice, diagnosis, or treatment. Always consult your physician or a qualified healthcare provider before making changes to your health routine or treatment plan.

    Medically reviewed by our editorial health team. Content follows evidence-based standards aligned with CDC, NIH, and American Cancer Society guidelines.

  • Cervical Health: HPV, Pap Smears & Prevention Guide

    Cervical Health: HPV, Pap Smears & Prevention Guide

    Cervical cancer is one of the most preventable cancers in women — yet thousands of American women are still diagnosed every year because of missed screenings or lack of awareness.

    Consider Maria, 42, a busy mother of three who had skipped her Pap smear for six years. Life kept getting in the way — work, kids, and the quiet assumption that if something were seriously wrong, she would know. When she finally went in for a routine checkup, her gynecologist found precancerous cervical cells early enough to treat successfully. Maria was lucky. Not every woman gets that chance.

    According to the American Cancer Society, approximately 13,820 new cases of invasive cervical cancer are diagnosed in the United States each year, and around 4,360 women die from it — most from cancers that were not caught early enough. The good news is that cervical health is highly manageable when you understand the risks, know your screening schedule, and stay informed about your options.

    In this guide, you will learn what cervical health really means, how human papillomavirus (HPV) plays a central role, what screening tests can detect problems early, and how you can take meaningful steps to protect yourself at every age.

    What Is Cervical Health — and Why Does It Matter?

    The cervix is the lower, narrow end of the uterus that connects to the vagina. It plays an important role in reproductive health, including menstruation, sexual function, and pregnancy. Cervical health refers to the overall condition of the cervical tissue and its ability to remain free of infection, inflammation, and abnormal cell changes.

    The most significant threat to cervical health is human papillomavirus, or HPV — a group of more than 200 related viruses, about 40 of which are spread through sexual contact. According to the CDC, HPV is the most common sexually transmitted infection in the United States. An estimated 79 million Americans are currently infected, and about 14 million new infections occur each year.

    Most HPV infections clear on their own without causing any harm. However, certain high-risk strains — particularly HPV 16 and HPV 18 — can cause persistent infection that leads to precancerous changes in cervical cells over time. If left undetected and untreated, these changes can progress to cervical cancer, typically over a period of 10 to 15 years.

    This slow progression is actually what makes cervical cancer so preventable. With regular screenings and the HPV vaccine, the disease can often be stopped before it starts or caught at a stage when treatment is most effective.

    Signs and Symptoms of Cervical Problems

    One of the most challenging aspects of cervical health is that early-stage cervical changes — including precancerous lesions — usually cause no symptoms at all. This is precisely why regular screenings are so essential.

    When symptoms do appear, they may indicate more advanced disease and should never be ignored. Be aware of the following:

    Early or less specific signs:

    • Unusual vaginal discharge (watery, bloody, or with an unpleasant odor)
    • Light bleeding or spotting between periods
    • Bleeding after sexual intercourse
    • Pelvic pain or discomfort that is new or unexplained
    • Longer or heavier menstrual periods than usual

    Signs that may indicate more advanced disease:

    • Persistent pelvic, back, or leg pain
    • Significant bleeding not related to menstruation
    • Swelling in the legs
    • Difficulty urinating or changes in bladder/bowel habits
    • Unexplained weight loss and fatigue

    A 2022 study published in the journal Gynecologic Oncology found that women who reported symptoms before diagnosis were more likely to present at a later stage, reinforcing the critical importance of screening before symptoms develop. This varies from person to person, but the pattern holds broadly across population data.

    Causes and Risk Factors for Cervical Cancer

    While HPV is the primary driver of cervical cancer — responsible for approximately 99% of all cases according to the NIH — not everyone who contracts HPV will develop cervical cancer. Several factors influence whether an infection becomes dangerous.

    Biological and lifestyle risk factors include:

    • Persistent high-risk HPV infection: Strains 16 and 18 account for about 70% of all cervical cancers
    • Smoking: Tobacco use doubles the risk of cervical cancer in women with HPV, as it weakens local immune defenses
    • Immunocompromised status: Women living with HIV are six times more likely to develop cervical cancer, per CDC data
    • Long-term use of oral contraceptives: Research suggests a modest increase in risk after five or more years, though the relationship is complex
    • Multiple sexual partners: Increases the likelihood of HPV exposure
    • History of other sexually transmitted infections (STIs): Including chlamydia or herpes
    • Early sexual activity: Particularly before age 18
    • Socioeconomic barriers to screening: Women without consistent access to healthcare are at significantly higher risk of late-stage diagnosis

    According to the American Cancer Society, Black women and Hispanic women in the US have higher cervical cancer incidence and mortality rates than non-Hispanic white women, largely due to disparities in access to screening and follow-up care — not inherent biological differences.

    Diagnosis: What to Expect from Cervical Screening

    Cervical cancer screening is one of the most well-established and effective cancer prevention tools in modern medicine. There are two primary tests used in the United States:

    1. The Pap Smear (Pap Test)
    This test collects cells from the surface of the cervix to check for abnormalities. An abnormal Pap result does not mean you have cancer — it means some cells looked unusual and need further evaluation. Abnormal findings are classified using a system that includes terms like ASCUS (atypical squamous cells of undetermined significance), LSIL (low-grade squamous intraepithelial lesion), and HSIL (high-grade squamous intraepithelial lesion), among others.

    2. The HPV Test
    This test checks directly for the presence of high-risk HPV strains in cervical cells. It is often performed alongside the Pap smear in what is called a co-test.

    Current screening guidelines from the US Preventive Services Task Force (USPSTF) as of 2026:

    • Women aged 21 to 29: Pap smear alone every 3 years
    • Women aged 30 to 65: Pap smear every 3 years, HPV test every 5 years, or co-test every 5 years
    • Women over 65: May stop screening if they have had adequate prior screening and no high-risk history
    • Women who have had a total hysterectomy (with cervix removed) for non-cancerous reasons: Typically do not need continued screening

    If a Pap or HPV test returns an abnormal result, your doctor may recommend a colposcopy — a closer examination of the cervix using a magnifying instrument — and possibly a biopsy to analyze the tissue more thoroughly.

    Treatment Options for Cervical Abnormalities and Cancer

    Treatment depends heavily on what is found and how advanced any changes are. Clinical evidence supports a range of approaches from watchful waiting to surgical intervention.

    For precancerous lesions (cervical dysplasia):

    • Watchful waiting / Active surveillance: For low-grade changes (LSIL), many physicians recommend closer monitoring since mild abnormalities often resolve on their own
    • LEEP (Loop Electrosurgical Excision Procedure): A thin wire loop carrying electrical current removes abnormal tissue; this is one of the most common treatments for high-grade lesions
    • Cryotherapy: Freezing abnormal cells to destroy them
    • Cone biopsy (Conization): Surgical removal of a cone-shaped section of abnormal cervical tissue

    For cervical cancer:

    • Surgery: Ranges from removing only the cancerous tissue to a hysterectomy depending on the stage
    • Radiation therapy: Often used in combination with chemotherapy for locally advanced disease
    • Chemotherapy: Usually used alongside radiation; may also be used for metastatic disease
    • Immunotherapy and targeted therapy: Newer options, such as pembrolizumab (Keytruda), have been approved by the FDA for certain cases of recurrent or metastatic cervical cancer

    According to the National Cancer Institute, when cervical cancer is caught at the localized stage, the 5-year relative survival rate is approximately 92%. When it spreads to distant sites, that rate drops to around 19%. This underscores why early detection through screening is not just helpful — it is potentially lifesaving.

    It is also worth noting that cervical health is closely tied to overall hormonal and reproductive wellness. If you are navigating other women’s health conditions alongside cervical changes, speaking with your gynecologist about a comprehensive care plan is strongly recommended. For women managing hormonal concerns, our article on Menopause and Heart Health may offer useful context about how hormonal shifts affect overall health outcomes.

    Living With Cervical Health Concerns and Prevention Strategies

    The most powerful thing you can do for your cervical health is to stay engaged with preventive care. Clinical evidence overwhelmingly supports a few core strategies:

    1. Get the HPV Vaccine
    The HPV vaccine — available in the US as Gardasil 9 — protects against the nine most common high-risk and low-risk HPV strains, including types 16 and 18. The CDC’s Advisory Committee on Immunization Practices (ACIP) recommends routine vaccination for all preteens aged 11 to 12, with catch-up vaccination available through age 26. Adults aged 27 to 45 may also benefit from vaccination after discussing risks and benefits with their physician.

    Research suggests that countries with high HPV vaccination rates have seen dramatic reductions in cervical cancer diagnoses. A landmark study published in The Lancet found that among fully vaccinated women, cervical cancer rates fell by nearly 90%.

    2. Stay Current on Screenings
    Do not skip or postpone your Pap smear or HPV test. These appointments are brief, but they can catch serious problems years before they become life-threatening.

    3. Quit Smoking
    If you smoke, quitting significantly reduces your risk of persistent HPV infection and cervical cancer. Your primary care provider can connect you with effective cessation programs and resources.

    4. Practice Safer Sex
    Consistent condom use reduces — though does not eliminate — the risk of HPV transmission. Open communication with sexual partners about STI status is equally important.

    5. Support Your Immune System
    A well-functioning immune system is your body’s primary tool for clearing HPV naturally. Eating a nutrient-dense diet, managing chronic stress, getting adequate sleep, and treating underlying conditions like HIV or autoimmune disease are all relevant factors. For women interested in evidence-based approaches to stress support, our guide on Ashwagandha Benefits for Stress and Hormonal Health may be worth reviewing alongside your doctor’s recommendations.

    6. Know Your Family History
    While cervical cancer itself is not directly inherited, a family history of gynecological cancers may affect your overall screening strategy and risk assessment.

    When to Call Your Doctor — and Emergency Warning Signs

    Some symptoms require prompt attention and should never be dismissed or attributed to normal variation without professional evaluation.

    Schedule a non-emergency appointment if you notice:

    • Any new or unusual vaginal discharge that persists more than a week
    • Light spotting after sex on more than one occasion
    • Pelvic discomfort without an obvious cause
    • An overdue Pap smear (more than 3 to 5 years since your last one)
    • Questions or concerns following an abnormal screening result

    Seek immediate or urgent medical care if you experience:

    • Heavy unexplained vaginal bleeding that soaks through more than one pad per hour
    • Severe pelvic or lower abdominal pain
    • Sudden inability to urinate or significant urinary pain
    • Significant unexplained weight loss combined with fatigue and pelvic symptoms
    • Any symptom that appears suddenly and feels unlike anything you have experienced before

    What to tell your doctor at your next visit: Be prepared to share your full screening history, current medications, smoking status, sexual history (as relevant), and any symptoms you have noticed, even if they seem minor. Honest, complete information allows your provider to give you the most accurate assessment.

    Frequently Asked Questions About Cervical Health and HPV

    Q: Can I get HPV even if I have only had one sexual partner?
    Yes. HPV is extremely common, and because it can remain dormant for years before causing detectable changes, it is possible to contract it from a single partner or to have it detected long after the original exposure. This is not a reflection of your or your partner’s behavior — it is simply how the virus behaves biologically.

    Q: If my HPV test comes back positive, does that mean I will get cervical cancer?
    Not at all. A positive HPV test means you currently have a detectable HPV infection. Most HPV infections — including high-risk strains — are cleared by the immune system within one to two years. Your doctor will use the result in combination with your Pap smear findings to determine the appropriate next steps, which may simply be closer monitoring.

    Q: I had the HPV vaccine years ago. Do I still need Pap smears?
    Yes, absolutely. The HPV vaccine does not protect against all strains of HPV, and it does not replace the need for regular cervical cancer screening. Most physicians recommend that vaccinated women follow the same screening schedule as unvaccinated women based on current USPSTF guidelines.

    Q: Is it safe to get a Pap smear during pregnancy?
    Yes, Pap smears are safe during pregnancy and are commonly performed at the first prenatal visit if you are due for one. Your OB-GYN will guide you on timing and any follow-up care needed based on results.

    Q: My mother had cervical cancer. Does that increase my risk?
    Having a first-degree relative with cervical cancer may modestly increase your risk, possibly because of shared environmental factors or some immune system characteristics. It is worth mentioning your family history to your gynecologist, who may recommend a more vigilant screening schedule as a precaution. You might also find it helpful to review our article on Uterine Fibroids for broader context on gynecological conditions that can sometimes cluster in families.

    Conclusion

    Cervical health is one of the areas of women’s health where science has given us genuinely powerful tools — a preventive vaccine, reliable screening tests, and effective treatments for early-stage disease. The gap between what is possible and what is actually achieved often comes down to access, awareness, and follow-through.

    You do not have to be a medical expert to protect yourself. You simply need to stay connected with your healthcare provider, keep up with your screenings, and speak up when something feels off. Whether you are 30 or 65, it is never too early or too late to take cervical health seriously.

    Talk to your doctor about where you stand with your current screening schedule, whether the HPV vaccine might still be appropriate for you, and what steps make the most sense for your individual situation. Your cervical health is worth the conversation.


    Medical Disclaimer: This article is for informational and educational purposes only. It does not constitute medical advice, diagnosis, or treatment. Always consult your physician or a qualified healthcare provider before making changes to your health routine or treatment plan.

    Medically reviewed by our editorial health team. Content follows evidence-based standards aligned with CDC and NIH guidelines.

  • Menopause and Heart Health: What Every Woman Must Know

    Menopause and Heart Health: What Every Woman Must Know

    Menopause and Heart Health: What Every Woman Must Know

    After estrogen drops, cardiovascular risk rises — and most women never see it coming.

    Linda, 54, considered herself healthy. She exercised three times a week, kept her weight in check, and had never smoked. Then, two years after her last menstrual period, her doctor delivered a surprise: her LDL cholesterol had jumped 28 points in a single year, and her blood pressure was creeping into the borderline range. No symptoms. No warning. Just numbers that told a story her body hadn’t voiced yet.

    Her story is far from unusual. According to the American Heart Association, heart disease is the leading cause of death in women in the United States — responsible for 1 in every 3 female deaths annually. Yet women are frequently undertreated and underdiagnosed, in part because menopause-related cardiovascular changes often unfold quietly, without the dramatic warning signs many expect.

    In this guide, you will learn exactly how menopause reshapes your cardiovascular risk, what symptoms and lab values to watch for, and what evidence-based strategies — medical and lifestyle — can meaningfully protect your heart in the years ahead.

    What Is the Menopause-Heart Health Connection?

    Menopause is the natural biological transition that occurs when a woman’s ovaries stop producing eggs and estrogen levels decline substantially. It is officially defined as 12 consecutive months without a menstrual period, typically occurring between ages 45 and 55. The average age of natural menopause in the United States is 51, according to the NIH.

    What many women don’t realize is that estrogen is not just a reproductive hormone — it plays a critical protective role in the cardiovascular system. Estrogen helps keep blood vessels flexible, supports healthy cholesterol levels by raising HDL ("good" cholesterol) and lowering LDL ("bad" cholesterol), reduces arterial inflammation, and helps regulate blood pressure.

    When estrogen levels fall during menopause, these protective effects diminish. Research published in Circulation, the journal of the American Heart Association, confirms that women’s cardiovascular risk accelerates significantly in the years following menopause — narrowing the long-standing gap between men’s and women’s heart disease rates.

    This doesn’t mean heart disease is inevitable. It means this transition is a critical window for prevention and proactive monitoring.

    Signs and Symptoms That May Signal Cardiovascular Changes

    One of the challenges of menopause-related heart risk is that many early cardiovascular changes produce no obvious symptoms. However, some signs overlap with menopause itself, making them easy to dismiss.

    Early and common warning signs to discuss with your doctor:

    • Heart palpitations (racing, fluttering, or irregular heartbeat) — common during perimenopause
    • Increased fatigue during exercise that was once manageable
    • Shortness of breath with mild exertion
    • Persistent headaches or new onset of high blood pressure readings
    • Noticeable weight gain around the abdomen, even without dietary changes
    • Elevated fasting blood sugar levels at routine labs
    • Cholesterol panel changes: rising LDL, falling HDL, rising triglycerides

    Advanced or urgent warning signs — seek immediate care:

    • Chest tightness, pressure, or pain
    • Pain radiating to the jaw, arm, back, or neck
    • Sudden dizziness or loss of balance
    • Unexplained nausea or cold sweats (women’s heart attack symptoms differ from men’s)
    • Sudden severe headache without cause
    • Fainting or near-fainting episodes

    A 2022 study published in the Journal of the American College of Cardiology found that palpitations during perimenopause were associated with a statistically higher rate of atrial fibrillation — a heart rhythm disorder — in women over 50. Always report new palpitations to your physician, even if they feel "normal" for this stage of life.

    Causes and Risk Factors After Menopause

    The cardiovascular risk that builds during and after menopause is driven by a combination of hormonal, metabolic, and lifestyle factors. Understanding your specific risk profile helps you and your doctor craft the most targeted prevention plan.

    Hormonal factors:

    • Declining estrogen leads directly to less favorable lipid profiles and stiffer arteries
    • Rising FSH (follicle-stimulating hormone) has been independently linked to increased coronary artery disease risk in some studies
    • Reduced progesterone may affect blood vessel tone and inflammatory markers

    Metabolic changes:

    • Visceral fat (fat stored around internal organs) increases after menopause, even without weight gain on the scale
    • Insulin sensitivity declines, raising fasting glucose and increasing type 2 diabetes risk — which is itself a major cardiac risk factor
    • Blood pressure tends to rise in postmenopausal women, partly due to arterial stiffness

    Pre-existing and lifestyle risk factors that worsen after menopause:

    • Smoking (doubles cardiovascular risk in menopausal women)
    • Physical inactivity
    • Family history of early heart disease
    • History of preeclampsia, gestational diabetes, or preterm birth (these are recognized independent cardiac risk factors for women, per the AHA)
    • History of autoimmune conditions such as lupus or rheumatoid arthritis
    • Chronic stress and depression

    According to the CDC, nearly 60% of American women over 55 have high blood pressure — a rate nearly equal to men in that same age bracket, compared to significantly lower rates in younger women. That narrowing reflects the direct impact of hormonal changes on vascular health.

    Diagnosis: What to Expect From Your Doctor

    Cardiovascular risk assessment after menopause requires more than a basic annual physical. Clinical evidence increasingly supports a more comprehensive approach for women in this life stage.

    Core tests and screenings your doctor may order or discuss:

    • Fasting lipid panel — measures total cholesterol, LDL, HDL, and triglycerides; should be done annually or more frequently if trending unfavorably
    • Blood pressure monitoring — at every visit; home monitoring may also be recommended
    • Fasting glucose and HbA1c — screens for insulin resistance and diabetes
    • Body mass index (BMI) and waist circumference — visceral fat is a specific risk marker; a waist circumference above 35 inches in women is considered a metabolic risk indicator
    • High-sensitivity CRP (C-reactive protein) — a blood marker for systemic inflammation, which drives arterial plaque buildup
    • Coronary artery calcium (CAC) score — a low-radiation CT scan that detects calcium deposits in coronary arteries; increasingly recommended for women in their 50s who fall into intermediate risk categories
    • Thyroid function (TSH) — hypothyroidism, more common in women, can mimic and worsen cardiovascular risk

    The American College of Cardiology and AHA guidelines now specifically recommend that clinicians ask women about pregnancy-related complications as part of cardiovascular risk history — a question that was historically overlooked.

    If you haven’t had a dedicated conversation with your doctor about your post-menopause heart risk profile, request one. This is not an area where a "wait and see" approach serves you well.

    Treatment Options: What the Evidence Supports

    Treatment for menopause-related cardiovascular risk is highly individualized. Most physicians recommend a combination of medical interventions and lifestyle modifications tailored to your specific lab values, symptoms, and history.

    Medical Treatments

    Statins: If LDL cholesterol rises significantly after menopause and lifestyle changes alone aren’t sufficient, your doctor may consider a statin medication. Research suggests statins reduce cardiovascular events in postmenopausal women with elevated cholesterol or existing risk factors. The decision to start a statin is individualized — based on 10-year cardiovascular risk calculators, lab trends, and patient preferences.

    Antihypertensives: If blood pressure consistently reads 130/80 mmHg or above (Stage 1 hypertension per current AHA/ACC guidelines), medication may be warranted alongside lifestyle measures. Several drug classes are available, and your doctor will choose based on your complete health picture.

    Menopausal Hormone Therapy (MHT): The role of hormone therapy in cardiovascular health is nuanced and has evolved significantly since the early 2000s. Current evidence from the Menopause Society (formerly NAMS) and the Endocrine Society suggests that MHT initiated within 10 years of menopause or before age 60 in healthy women without contraindications may have a favorable cardiovascular effect — reducing risk of new-onset diabetes, slowing arterial stiffness, and improving lipid profiles. MHT is not appropriate for everyone and carries its own risks depending on personal and family history. This is a conversation to have carefully with your gynecologist or internist, not a decision to make based on generalized headlines.

    Blood sugar management: If insulin resistance or prediabetes is identified, your doctor may recommend metformin or other agents in addition to dietary changes, depending on your full risk picture.

    Lifestyle Modifications — With Strong Evidence

    Lifestyle changes remain the foundation of cardiovascular risk reduction at every stage, and their impact in menopausal women is well-documented.

    • Aerobic exercise: Clinical evidence from the NIH indicates that 150 minutes per week of moderate-intensity aerobic activity (brisk walking, swimming, cycling) significantly improves blood pressure, cholesterol, and insulin sensitivity in postmenopausal women. Resistance training twice weekly adds further metabolic benefit.
    • Dietary pattern: The Mediterranean diet — rich in olive oil, fish, legumes, vegetables, and whole grains — has the strongest evidence base for cardiovascular protection in women. The PREDIMED trial showed a 30% reduction in major cardiovascular events among high-risk adults following this pattern.
    • Sodium reduction: Limiting sodium to under 2,300 mg daily supports healthy blood pressure. Many postmenopausal women see meaningful blood pressure improvements from dietary sodium reduction alone.
    • Smoking cessation: If you smoke, stopping is the single most impactful cardiovascular intervention available. Cardiovascular risk begins to drop within 24 hours of quitting and continues to improve for years.
    • Stress management: Chronic psychological stress elevates cortisol, promotes inflammation, and has been directly linked to worse cardiovascular outcomes in women. Mindfulness-based stress reduction (MBSR), therapy, and structured relaxation practices are supported by growing clinical evidence.

    For women interested in complementary support, our article on Ashwagandha Benefits: Stress, Sleep & Hormonal Health reviews the evidence on adaptogenic herbs — which should always be discussed with your doctor before use.

    Living With Menopause While Protecting Your Heart

    Managing cardiovascular health during and after menopause is an ongoing practice, not a single intervention. Here’s what a sustainable, heart-protective daily routine looks like in practical terms:

    • Monitor your numbers: Know your blood pressure, LDL, HDL, fasting glucose, and waist circumference — and track trends over time, not just single readings.
    • Prioritize sleep: Sleep disruption is extremely common in menopause and directly worsens blood pressure, blood sugar regulation, and inflammation. Our guide on Sleep After 50: Why It Changes and How to Sleep Better offers evidence-based strategies for this life stage.
    • Move consistently: Aim for activity every day — even a 20-minute walk lowers cardiovascular risk. Sedentary behavior between workouts has independent negative effects, separate from exercise time.
    • Watch the alcohol: The AHA recommends no more than one drink per day for women, and current research suggests even this level may carry some cardiovascular risk for certain individuals.
    • Schedule annual preventive labs: Don’t wait for symptoms. Cardiovascular disease in women is frequently silent until a serious event occurs.
    • Communicate openly with your care team: Bring a list of all supplements, over-the-counter medications, and symptoms to each appointment. Many women underreport symptoms or attribute them to "just menopause."

    For women managing heart health concerns, our overview of Heart Health After 60: Risks, Signs & How to Stay Strong provides additional guidance relevant to this population.

    When to Call Your Doctor — And When to Call 911

    Call your doctor within 1-2 days if you notice:

    • New or worsening palpitations, especially with dizziness
    • Blood pressure readings consistently above 130/80 mmHg at home
    • Unexplained shortness of breath during normal daily activities
    • Significant fatigue that limits your usual routine
    • Lab results showing a notable change in cholesterol, blood sugar, or CRP

    Call 911 immediately if you experience:

    • Chest pain, pressure, tightness, or squeezing — even mild
    • Pain spreading to the arm, jaw, back, or stomach
    • Sudden severe shortness of breath
    • Fainting, sudden confusion, or difficulty speaking
    • Sudden numbness or weakness on one side of the body (potential stroke)
    • Cold sweat, nausea, and lightheadedness together

    Women’s heart attack symptoms are frequently atypical — meaning they may not match the "classic" chest-clutching image. A 2019 analysis from the AHA confirmed that women are significantly more likely than men to experience nausea, back pain, jaw pain, or extreme fatigue as primary heart attack symptoms. Do not talk yourself out of emergency care because your symptoms seem subtle.

    Frequently Asked Questions

    Q: Does menopause directly cause heart disease?
    Menopause itself does not directly cause heart disease, but the hormonal changes that accompany it — particularly the decline in estrogen — significantly alter cardiovascular risk factors. Most physicians view menopause as a time of accelerated risk accumulation that requires proactive monitoring and, when appropriate, intervention.

    Q: Should all menopausal women take hormone therapy to protect their hearts?
    No. Menopausal hormone therapy (MHT) is not universally recommended for cardiovascular protection. Current guidelines suggest it may be appropriate and beneficial for some women — particularly those under 60 or within 10 years of menopause — but it carries risks including blood clots, stroke, and breast cancer in certain populations. This decision must be individualized with your physician.

    Q: Can regular exercise really make a significant difference in heart risk after menopause?
    Yes. Clinical evidence indicates that regular moderate aerobic exercise reduces cardiovascular mortality risk in postmenopausal women by approximately 30-35%, according to research reviewed by the NIH. Consistency matters more than intensity — daily movement is the goal.

    Q: Is heart disease risk in women the same as in men after menopause?
    Not exactly. While the gap narrows significantly, women tend to develop heart disease 10-15 years later than men on average. However, women who experience early menopause (before age 45) — whether natural or surgical — face a substantially elevated risk that more closely resembles the male pattern, according to data from the Nurses’ Health Study.

    Q: What cholesterol levels should I aim for after menopause?
    General targets recommended by most physicians include: LDL below 100 mg/dL (or lower if you have existing risk factors), HDL above 50 mg/dL for women, and triglycerides below 150 mg/dL. However, your individual targets should be set by your doctor based on your complete cardiovascular risk assessment — not generalized numbers alone.

    Conclusion

    Menopause is a natural life transition — but the cardiovascular changes it triggers are real, measurable, and clinically significant. The good news is that this transition also represents one of the most powerful windows for prevention. When women understand their changing risk profile and take proactive steps — through regular monitoring, targeted lifestyle changes, and open conversations with their healthcare team — heart disease outcomes can be meaningfully improved.

    You don’t need to be afraid of menopause. But you do need to be informed. Your heart is working hard for you every minute of every day. This is the moment to start working equally hard for it.

    Talk to your doctor about a comprehensive cardiovascular risk assessment if you haven’t had one recently — especially if you are in perimenopause or postmenopause. Knowledge is your most protective tool.


    Medical Disclaimer: This article is for informational and educational purposes only. It does not constitute medical advice, diagnosis, or treatment. Always consult your physician or a qualified healthcare provider before making changes to your health routine or treatment plan.

    Medically reviewed by our editorial health team. Content follows evidence-based standards aligned with CDC, NIH, and American Heart Association guidelines.

  • Uterine Fibroids: Symptoms, Causes & Treatment Options

    Uterine Fibroids: Symptoms, Causes & Treatment Options

    Millions of American women live with uterine fibroids — many without even knowing it. Here is what every woman should understand about this common condition.

    Maria, 44, had been dealing with increasingly heavy periods for two years. She went through two boxes of pads each cycle, canceled plans because of cramping, and chalked it all up to “just getting older.” It was not until a routine pelvic exam that her gynecologist discovered she had three uterine fibroids — the largest the size of a golf ball.

    Maria’s experience is far from unusual. According to the National Institutes of Health, uterine fibroids affect up to 80% of women by the age of 50, making them the most common noncancerous tumors in women of reproductive age. Yet many women remain undiagnosed, often dismissing symptoms as normal menstrual variation.

    In this guide, you will learn exactly what uterine fibroids are, how to recognize the signs, what causes them, and what your treatment options look like in 2026 — from the most conservative approaches to minimally invasive procedures. Knowledge is the first step toward feeling better.

    What Are Uterine Fibroids?

    Uterine fibroids — also called leiomyomas or myomas — are noncancerous (benign) growths that develop from the muscle tissue of the uterus. They are not associated with an increased risk of uterine cancer and almost never become malignant.

    Fibroids can range dramatically in size. Some are as small as a seed; others can grow to the size of a grapefruit or larger. A woman may have a single fibroid or many, and their location within the uterus matters a great deal when it comes to symptoms.

    There are four main types based on location:

    • Intramural fibroids: Grow within the muscular wall of the uterus — the most common type
    • Submucosal fibroids: Develop just under the lining of the uterine cavity — most likely to cause heavy bleeding and fertility issues
    • Subserosal fibroids: Grow on the outer surface of the uterus, sometimes pressing on nearby organs
    • Pedunculated fibroids: Attached to the uterus by a thin stalk, either inside or outside

    The CDC reports that uterine fibroids account for approximately 200,000 hysterectomies per year in the United States, making them the leading reason women undergo this major surgery. However, hysterectomy is far from the only — or necessarily the best — option for most women.

    Signs and Symptoms of Uterine Fibroids

    Here is one of the most important facts about fibroids: many women have them and feel absolutely nothing. Research suggests that up to 50% of women with fibroids are asymptomatic, meaning their fibroids are discovered only during routine imaging or pelvic exams.

    For those who do experience symptoms, the severity tends to depend on the size, number, and location of the fibroids.

    Early or mild symptoms may include:

    • Slightly heavier or longer menstrual periods
    • Mild pelvic pressure or a sensation of fullness
    • Frequent urination if the fibroid presses on the bladder
    • Lower back discomfort
    • Constipation if the fibroid presses on the rectum

    More advanced or serious symptoms may include:

    • Extremely heavy menstrual bleeding (soaking a pad or tampon every hour for several hours)
    • Periods lasting longer than seven days
    • Severe pelvic pain or pressure
    • Iron-deficiency anemia caused by excessive blood loss
    • Pain during sexual intercourse
    • Difficulty getting pregnant or recurrent miscarriages
    • Visible abdominal enlargement from a large fibroid

    A 2021 study published in the American Journal of Obstetrics and Gynecology found that Black women are two to three times more likely to develop fibroids than white women, tend to develop them at a younger age, and experience more severe symptoms — highlighting that this is not a one-size-fits-all condition. This variation from person to person reinforces the importance of individualized medical care.

    Causes and Risk Factors

    Researchers have not yet pinpointed a single cause of uterine fibroids, but clinical evidence points to a combination of genetic, hormonal, and environmental factors.

    Hormonal influence: Estrogen and progesterone — the hormones that regulate your menstrual cycle — appear to stimulate fibroid growth. This is why fibroids often grow rapidly during pregnancy (when hormone levels are high) and tend to shrink after menopause (when hormone production drops). Fibroids contain more estrogen and progesterone receptors than normal uterine muscle cells.

    Genetic predisposition: If your mother, sister, or grandmother had fibroids, your risk is significantly higher. Certain genetic changes found in fibroid cells differ from normal uterine muscle cells, suggesting a hereditary component.

    Race and ethnicity: As noted above, Black women in the US face a disproportionate fibroid burden. NIH-funded research indicates this disparity may involve a combination of genetic factors, higher rates of stress exposure, differences in vitamin D levels, and unequal access to early diagnosis and treatment.

    Other known risk factors include:

    • Obesity — excess fat tissue produces additional estrogen
    • Early onset of menstruation (before age 10)
    • A diet high in red meat and low in green vegetables and fruit
    • Vitamin D deficiency — research suggests lower vitamin D levels are associated with higher fibroid risk. For more on this topic, see our article on Vitamin D Deficiency: Symptoms, Causes & Natural Solutions
    • Alcohol consumption
    • Hypertension (high blood pressure)
    • Never having been pregnant

    Notably, having a healthy gut microbiome may play an indirect role in estrogen regulation — an active area of emerging research — though no definitive clinical guidance yet exists in this area.

    Diagnosis: What to Expect

    If your doctor suspects uterine fibroids based on your symptoms or a routine pelvic exam, the next step is imaging. The good news: diagnosing fibroids is typically straightforward and does not involve invasive procedures.

    Pelvic ultrasound is the most common first-line diagnostic tool. It uses sound waves to create images of your uterus, allowing your doctor to identify the size, number, and location of fibroids. This test is painless and widely available.

    Transvaginal ultrasound involves a small probe placed gently inside the vagina to provide clearer, closer images of the uterus — particularly useful for detecting smaller fibroids.

    MRI (Magnetic Resonance Imaging) provides the most detailed view of fibroid size and location and is often used when planning surgery or other procedures. Research suggests MRI is more accurate than ultrasound for mapping multiple or deeply embedded fibroids.

    Hysteroscopy allows your doctor to look directly inside the uterine cavity using a thin, lighted tube. This is particularly helpful for detecting submucosal fibroids and is sometimes performed as part of treatment.

    Sonohysterography (also called a saline infusion sonogram) uses sterile saline to expand the uterus during an ultrasound, giving a clearer view of the inner uterine wall.

    When should you seek a diagnosis? If you are experiencing heavy periods that interfere with your daily life, pelvic pressure, pain during sex, or any symptoms you cannot explain, do not wait. Early diagnosis gives you more options.

    Treatment Options for Uterine Fibroids

    Treatment for uterine fibroids is not one-size-fits-all. Your doctor will consider your symptoms, the size and location of your fibroids, your age, whether you want to have children in the future, and your overall health. Most physicians recommend starting with the most conservative approach and escalating only if needed.

    Watchful Waiting

    If your fibroids are small and causing few or no symptoms, your doctor may recommend monitoring them over time — especially if you are approaching menopause, after which fibroids typically shrink on their own. This involves regular pelvic exams and ultrasounds.

    Medications

    Hormonal therapies are often the first medical approach. Options include:

    • GnRH agonists (gonadotropin-releasing hormone agonists) temporarily put the body into a menopause-like state, reducing estrogen and shrinking fibroids. They are typically used short-term before surgery to reduce fibroid size. The FDA approved relugolix combination therapy (Myfembree) for fibroid-related heavy menstrual bleeding, offering a newer oral option.
    • Progestin-releasing IUDs can reduce heavy menstrual bleeding caused by fibroids, though they do not shrink the fibroids themselves
    • Oral contraceptives may help control heavy bleeding in some women
    • Tranexamic acid is a non-hormonal medication taken during your period to reduce excessive bleeding
    • NSAIDs like ibuprofen can help with pain management

    Minimally Invasive Procedures

    For women who want to treat fibroids without major surgery:

    • Uterine fibroid embolization (UFE): A radiologist threads a thin tube into the arteries supplying the fibroids and injects tiny particles that block blood flow, causing fibroids to shrink. Clinical evidence indicates UFE is effective for most women and preserves the uterus. Recovery is typically one to two weeks.
    • Radiofrequency ablation (RFA): Uses heat energy to destroy fibroid tissue. The Acessa procedure (laparoscopic RFA) has been FDA-approved and clinical trials show significant reductions in bleeding and symptom burden.
    • MRI-guided focused ultrasound (MRgFUS): A noninvasive option using focused ultrasound waves to destroy fibroid tissue while you are inside an MRI scanner. Best suited for women with a small number of fibroids.
    • Myomectomy: Surgical removal of the fibroids while preserving the uterus — the preferred option for women who still want to conceive. It can be performed laparoscopically, robotically, or through an open incision depending on fibroid size and location.

    Hysterectomy

    Surgical removal of the uterus is the only permanent cure for fibroids and eliminates any possibility of recurrence. It is appropriate for women who have completed their families and have severe, treatment-resistant symptoms. However, most physicians recommend exhausting less invasive options first.

    Lifestyle as a Complement

    While lifestyle changes alone will not eliminate fibroids, research suggests they may support symptom management. Maintaining a healthy weight, eating a diet rich in fruits, vegetables, and whole grains, limiting red meat and alcohol, and managing stress can all play a supportive role. Some studies also point to regular physical activity as helpful for reducing estrogen levels over time.

    Living With Uterine Fibroids: Practical Guidance

    If you have been diagnosed with fibroids, day-to-day management is very much achievable. Here are strategies most clinicians recommend:

    • Track your symptoms: Keep a period diary noting flow heaviness, duration, pain levels, and any other changes. This information is invaluable at medical appointments.
    • Manage anemia: If heavy bleeding has caused iron-deficiency anemia, work with your doctor on iron supplementation and consider iron-rich foods like lean red meat, beans, lentils, and leafy greens.
    • Address pain proactively: A heating pad, NSAIDs taken on schedule (not just when pain peaks), and rest during heavy flow days can make a real difference.
    • Prioritize mental health: Living with chronic pain and unpredictable bleeding takes an emotional toll. Connecting with a therapist or a fibroid support group — many are available online through organizations like the White Dress Project — can help significantly.
    • Fertility planning: If you hope to conceive, discuss your fibroid type and location with a reproductive endocrinologist. Submucosal fibroids in particular may interfere with implantation, but treatment can often restore fertility prospects.

    For women managing related hormonal conditions alongside fibroids, understanding the link between conditions like endometriosis and fibroid co-occurrence may be helpful when speaking with your care team.

    When to Call Your Doctor — and When to Go to the ER

    Many fibroid symptoms, while disruptive, are not medical emergencies. But some signs require prompt attention.

    Contact your doctor soon if you experience:

    • Periods that are suddenly heavier or longer than usual
    • Pelvic pain that is new, worsening, or not responding to over-the-counter treatment
    • Fatigue, shortness of breath, or dizziness that could indicate anemia
    • Difficulty urinating or complete inability to urinate
    • Changes in bowel habits linked to pelvic pressure
    • Abdominal swelling you cannot explain

    Go to the emergency room immediately if you have:

    • Sudden, severe pelvic pain (which may indicate a fibroid twisting on its stalk — a condition called torsion)
    • Uncontrolled vaginal bleeding that soaks through a pad every 15 to 30 minutes
    • Signs of severe anemia: extreme weakness, fainting, rapid heartbeat, or confusion
    • High fever with pelvic pain (which could suggest infection after a procedure)

    When you see your doctor at a routine visit, bring your symptom diary, a list of all medications and supplements you are taking, and any questions you have prepared in advance. Do not hesitate to ask about all available treatment options — including the newer, minimally invasive ones.

    Frequently Asked Questions About Uterine Fibroids

    Can uterine fibroids turn into cancer?
    This is one of the most common fears — and the reassurance is clear. Fibroids are benign tumors and very rarely become cancerous. A type of cancer called uterine leiomyosarcoma can occur in the uterus, but current evidence indicates it does not arise from pre-existing fibroids. The Mayo Clinic and NIH both confirm that the risk of a fibroid being or becoming cancerous is less than 1 in 1,000.

    Will uterine fibroids go away on their own?
    Fibroids often do shrink — but typically not until after menopause, when estrogen levels drop naturally. Younger women are unlikely to see spontaneous resolution. The timeline and degree of shrinkage vary considerably from person to person.

    Can I still get pregnant if I have fibroids?
    Many women with fibroids conceive and deliver healthy babies without any intervention. However, certain types — particularly submucosal fibroids that distort the uterine cavity — may interfere with implantation or increase miscarriage risk. If you are trying to conceive, a reproductive specialist can assess whether treatment is advisable before you attempt pregnancy.

    Are fibroids more common in Black women — and why?
    Yes. Research consistently shows Black women are diagnosed with fibroids at higher rates, at younger ages, and with more severe symptoms. NIH researchers believe multiple factors are involved: genetic variants, earlier onset of puberty, differences in vitamin D status, greater cumulative stress exposure, and historically unequal access to medical care. Advocacy for equitable fibroid research and treatment remains an active public health priority in the US.

    What is the least invasive treatment for fibroids?
    For women with symptoms, uterine fibroid embolization (UFE) and radiofrequency ablation are among the least invasive effective options that preserve the uterus. Medication can also help manage symptoms without surgery. The right choice depends on your individual situation, which is why a thorough discussion with your gynecologist or an interventional radiologist is essential.

    Conclusion

    Uterine fibroids are extraordinarily common — and for far too long, women have been told that heavy, painful periods are simply something to endure. They are not. Whether your fibroids require monitoring, medication, or a procedure, you have more options than ever before, and the landscape of minimally invasive treatment continues to expand.

    The most important step is not to stay silent. Talk to your gynecologist, advocate for imaging if your symptoms feel off, and get a second opinion if a treatment plan does not feel right for you. You deserve care that fits your life, your goals, and your body.

    Every woman’s experience with fibroids is different — which is exactly why personalized, evidence-based medical guidance is so important. You do not have to navigate this alone.


    This article is for informational and educational purposes only. It does not constitute medical advice, diagnosis, or treatment. Always consult your physician or a qualified healthcare provider before making changes to your health routine or treatment plan.

    Medically reviewed by our editorial health team. Content follows evidence-based standards aligned with CDC and NIH guidelines.
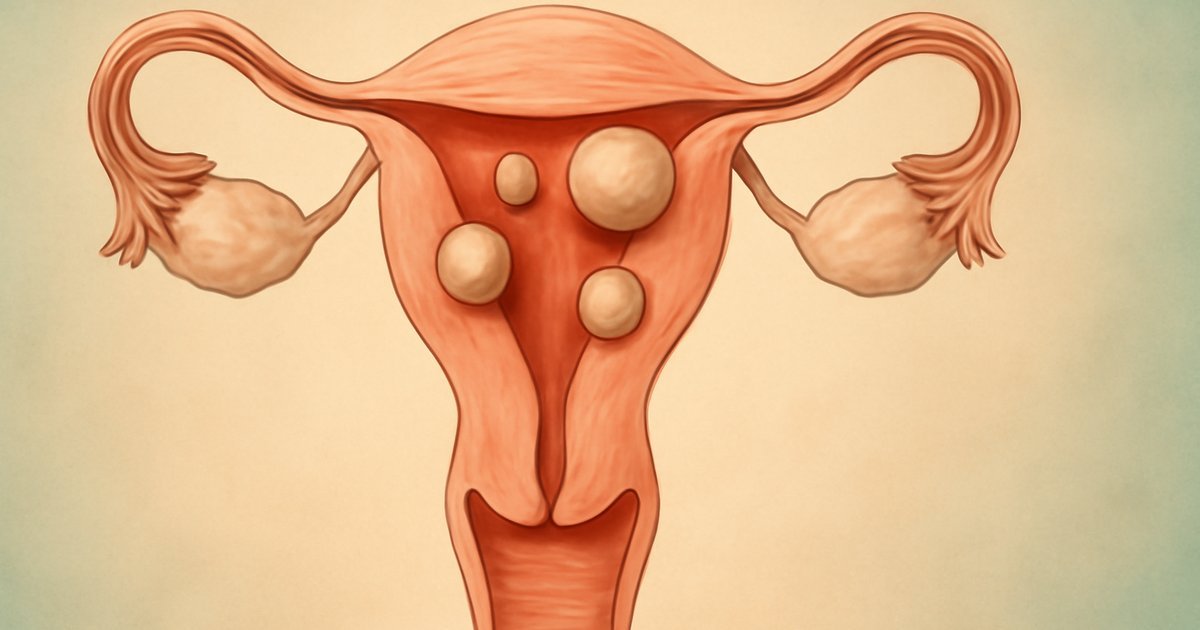
  • Endometriosis: Symptoms, Causes & Treatment Options

    Endometriosis: Symptoms, Causes & Treatment Options

    Endometriosis: Symptoms, Causes & Treatment Options

    One of the most underdiagnosed conditions in women’s health — and one you deserve to fully understand.

    When Lauren, 34, finally received her endometriosis diagnosis, she had already spent nearly a decade being told her pain was "just bad cramps." She had missed work, canceled plans, and quietly wondered if she was imagining it all. She wasn’t. According to the Office on Women’s Health (part of the U.S. Department of Health & Human Services), endometriosis affects approximately 11% of American women between the ages of 15 and 44 — roughly 6.5 million people — yet the average time from symptom onset to diagnosis is still estimated at seven to ten years.

    That delay has real consequences: chronic pelvic pain, fertility challenges, reduced quality of life, and mounting frustration. The good news is that once diagnosed, endometriosis is a manageable condition with a growing range of medical and surgical options.

    In this guide, you’ll learn exactly what endometriosis is, how it’s recognized and diagnosed, what drives it, and what current evidence says about treatment — so you can walk into your next doctor’s appointment informed and ready to advocate for yourself.


    What Is Endometriosis?

    Endometriosis (pronounced en-doh-mee-tree-OH-sis) is a chronic inflammatory condition in which tissue similar to the endometrium — the lining that normally grows inside the uterus — develops outside of it. This misplaced tissue is often found on the ovaries, fallopian tubes, the outer surface of the uterus, and the tissue lining the pelvis. In rarer cases, it can appear on the bladder, bowel, or even distant organs.

    Here’s why that matters: like the uterine lining, this tissue responds to hormonal changes during the menstrual cycle. It thickens, breaks down, and attempts to bleed — but unlike menstrual blood, this tissue has nowhere to go. The result is inflammation, scarring (adhesions), and cysts (sometimes called "chocolate cysts" on the ovaries) that can disrupt normal anatomy and organ function.

    The American College of Obstetricians and Gynecologists (ACOG) classifies endometriosis into four stages (I through IV) based on location, extent, and depth of implants, as well as the presence of adhesions. Even Stage I can cause severe symptoms in some women, while Stage IV may be relatively silent in others — individual variation is a hallmark of this disease.

    Endometriosis is not a cancer, and it does not increase the risk of uterine cancer. However, research published in journals reviewed by the NIH suggests a modest association with certain ovarian cancer subtypes, which is one reason ongoing monitoring matters.


    Signs and Symptoms of Endometriosis

    The symptom picture of endometriosis is wide-ranging, which is part of why it takes so long to diagnose. Some women experience debilitating pain; others have no pain at all and only discover the condition when investigating infertility.

    Early or common symptoms include:

    • Painful periods (dysmenorrhea) — cramping that begins before and continues well after menstruation
    • Pelvic pain that persists outside of your menstrual cycle
    • Pain during or after sexual intercourse (dyspareunia)
    • Painful bowel movements or urination, especially during menstruation
    • Heavy menstrual bleeding or bleeding between periods
    • Bloating and abdominal distension, often called "endo belly"
    • Fatigue that feels disproportionate to activity level

    Symptoms that may indicate advanced or widespread disease:

    • Difficulty becoming pregnant (endometriosis accounts for up to 50% of infertility cases evaluated by the American Society for Reproductive Medicine)
    • Rectal bleeding or blood in urine during menstrual periods
    • Chronic lower back pain radiating to the legs
    • Nausea and vomiting surrounding the menstrual cycle
    • Bowel obstruction symptoms in rare, severe cases

    A landmark survey cited by the Endometriosis Foundation of America found that over 60% of women with the condition had their symptoms initially dismissed or misattributed — most often to primary dysmenorrhea (normal painful periods) or irritable bowel syndrome. This overlap with other conditions, including IBS, is an important reason why specialized evaluation is so valuable.


    Causes and Risk Factors

    Researchers still do not fully understand what causes endometriosis, but several theories have gained strong scientific support.

    The most widely accepted explanation is retrograde menstruation — where menstrual blood containing endometrial cells flows backward through the fallopian tubes into the pelvic cavity instead of exiting the body. Most women experience some retrograde flow, but in those with endometriosis, these cells implant and grow. Why some women’s immune systems fail to destroy these misplaced cells remains an active area of research at institutions like Johns Hopkins Medicine.

    Other proposed mechanisms include:

    • Immune system dysfunction: The body may not recognize and destroy endometrial tissue outside the uterus effectively
    • Surgical scarring: After procedures like cesarean sections, endometrial cells may attach to incision sites
    • Hormonal transport: Blood or lymphatic vessels may carry endometrial cells to distant sites
    • Embryonic cell transformation: Peritoneal cells may transform into endometrial-like cells under hormonal influence

    Known risk factors include:

    • Family history — having a mother or sister with endometriosis increases your risk up to 7–10 times (NIH data)
    • Never having given birth
    • Menstrual cycles shorter than 27 days or periods lasting more than 7 days
    • Starting menstruation before age 11
    • Low body mass index
    • Uterine abnormalities that impair normal menstrual flow

    It’s important to note that endometriosis occurs across all racial and ethnic groups, though research suggests certain disparities in diagnosis timing exist — a gap that clinicians and health advocates are actively working to close.


    Diagnosis: What to Expect

    If you suspect endometriosis, knowing what to expect during the diagnostic process can reduce anxiety and help you prepare meaningful questions for your provider.

    Initial evaluation typically involves a detailed medical and menstrual history, a pelvic exam, and imaging studies. Transvaginal ultrasound can detect ovarian cysts (endometriomas) and deep infiltrating endometriosis in some cases, but it cannot visualize all types of lesions. MRI (magnetic resonance imaging) offers more detailed imaging, particularly for deep endometriosis near the bladder or bowel.

    However, the only definitive way to diagnose endometriosis is through laparoscopy — a minimally invasive surgical procedure in which a thin camera is inserted through a small abdominal incision. During laparoscopy, a surgeon can directly visualize lesions, take biopsies for pathological confirmation, and often treat endometriosis in the same procedure.

    When to seek evaluation:

    • Pelvic pain that interferes with daily activities, work, or relationships
    • Menstrual cramps that don’t improve with over-the-counter pain relievers
    • Difficulty getting pregnant after 6–12 months of trying (depending on age)
    • Pain during sex that is new, worsening, or accompanied by other symptoms

    The Mayo Clinic advises against delaying evaluation, emphasizing that earlier diagnosis gives you more options and may help prevent disease progression and fertility complications.


    Treatment Options for Endometriosis

    There is currently no cure for endometriosis, but treatment can significantly reduce pain, slow disease progression, and improve fertility outcomes. Your treatment plan will depend on symptom severity, disease stage, your reproductive goals, and your response to prior therapies. This varies meaningfully from person to person.

    Medications

    Hormonal therapies are a cornerstone of endometriosis management. Because endometrial tissue is driven by estrogen, suppressing estrogen levels reduces lesion activity and pain. Options include:

    • Hormonal contraceptives (combined oral contraceptive pills, patch, ring, or hormonal IUDs) — often the first-line treatment. Clinical evidence from the NIH confirms their effectiveness in reducing painful periods and slowing disease progression.
    • Progestins — synthetic progesterone-like compounds that counter estrogen’s effects on endometrial tissue
    • GnRH agonists and antagonists — medications that induce a temporary, medically reversible "menopause-like" state to halt estrogen production. The FDA has approved newer GnRH antagonists specifically for endometriosis-associated pain.
    • Danazol — an older androgen-based therapy used less frequently today due to side effects

    Pain management with NSAIDs (nonsteroidal anti-inflammatory drugs like ibuprofen or naproxen) is often used alongside hormonal treatment to control discomfort. Your physician is the right person to guide appropriate dosing based on your specific situation.

    Surgery

    When medication does not adequately control symptoms, or when fertility is the primary concern, laparoscopic surgery to remove or ablate endometrial lesions and adhesions is recommended. Studies reviewed by the American Society for Reproductive Medicine show that surgical excision can improve natural conception rates in women with mild-to-moderate disease.

    In cases of severe, treatment-resistant disease in women who have completed childbearing, hysterectomy (removal of the uterus) with removal of the ovaries may be discussed — but this is considered a last resort, not a cure, since endometriosis can persist even after this procedure.

    Lifestyle Modifications as a Complement

    Research suggests that certain lifestyle strategies may help reduce inflammation and support overall wellbeing alongside medical treatment:

    • Anti-inflammatory diet: Clinical evidence indicates that diets rich in omega-3 fatty acids, fruits, vegetables, and fiber may help reduce endometriosis-related inflammation. Our detailed guide on omega-3 fatty acids covers the research on inflammation reduction in depth.
    • Regular moderate exercise: Physical activity may reduce estrogen levels and lower prostaglandin production (chemicals that drive cramping)
    • Stress reduction: Chronic stress amplifies pain perception. Evidence-backed approaches like mindfulness, yoga, and cognitive behavioral therapy (CBT) are used as adjuncts in many endometriosis care programs.
    • Pelvic floor physical therapy: Increasingly recommended by specialists at centers like Cleveland Clinic to address muscle tension and pain patterns associated with endometriosis

    Living With Endometriosis: Day-to-Day Management

    Managing a chronic condition like endometriosis is a long-term commitment — and it’s one that requires a team approach. Most specialists recommend building a care team that may include your OB-GYN, a reproductive endocrinologist, a pelvic pain specialist, and a mental health professional who understands chronic illness.

    Practical strategies that many women find helpful:

    • Keep a detailed symptom journal tracking pain levels, menstrual patterns, triggers, and treatment responses — this data is invaluable at medical appointments
    • Plan ahead for high-symptom days by adjusting schedules when possible and keeping a "flare kit" with prescribed or recommended pain management tools
    • Connect with patient communities such as those supported by the Endometriosis Foundation of America or ACOG’s patient resources — peer support is associated with better coping outcomes
    • Communicate openly with partners, family, and employers about your limitations without over-explaining — chronic conditions are legitimate medical realities

    It’s also worth noting the connection between endometriosis and mood. A 2023 analysis published in journals indexed by NIH’s PubMed found that women with endometriosis have significantly higher rates of anxiety and depression compared to the general population — likely driven by both chronic pain and the hormonal fluctuations involved. Addressing mental health as part of your care plan is not optional; it’s essential. Strategies for managing the stress response, including evidence-based approaches to stress management, may serve as useful complementary tools alongside your medical plan.


    When to Call Your Doctor or Seek Emergency Care

    While endometriosis symptoms are often chronic and cyclical, certain signs require prompt medical attention.

    Contact your doctor promptly if you experience:

    • A sudden change in the nature or severity of your pelvic pain
    • Fever accompanying pelvic pain (may indicate infection)
    • Inability to urinate or have a bowel movement
    • New or unexplained rectal bleeding
    • Significant pain that your usual medications are not controlling

    Go to the emergency room immediately if you have:

    • Sudden, severe abdominal or pelvic pain that is different from your usual endometriosis pain — this could indicate a ruptured ovarian cyst or other acute complication
    • Fainting, dizziness, or signs of internal bleeding
    • Fever above 101°F with pelvic pain and vomiting

    What to tell your doctor at your next scheduled visit:

    • Your current pain score on most days vs. your worst days
    • How symptoms are affecting work, sex life, sleep, and mood
    • Any treatments you’ve tried and how well they’ve worked
    • Whether you are trying to conceive now or planning to in the future — this changes treatment priorities significantly

    Frequently Asked Questions About Endometriosis

    Q: Can endometriosis be cured?
    A: Currently, there is no definitive cure for endometriosis. However, many women achieve significant, long-term symptom relief through hormonal therapy, surgery, or a combination of both. Research is ongoing, and treatment options continue to expand. The goal of care is to maximize quality of life and preserve fertility when desired.

    Q: Will endometriosis prevent me from getting pregnant?
    A: Not necessarily. Many women with endometriosis conceive naturally or with medical assistance. The impact on fertility depends on disease stage and location. Early treatment and consultation with a reproductive specialist can help you understand your individual outlook. According to the American Society for Reproductive Medicine, IVF (in vitro fertilization) is an effective option for many women with endometriosis-related infertility.

    Q: Does endometriosis get worse over time?
    A: Endometriosis is considered a progressive condition in many — though not all — women. Some experience stable or even improved symptoms over time, particularly after pregnancy or menopause (when estrogen levels naturally decline). Regular monitoring and consistent treatment adherence are the best tools for managing progression.

    Q: Is there a connection between endometriosis and perimenopause?
    A: Yes, and it’s an important one. As women approach menopause, estrogen levels begin to fluctuate, which can affect endometriosis symptoms. Some women notice symptom relief as they transition through perimenopause; others see symptoms persist or shift. Our in-depth guide on perimenopause symptoms and management covers this hormonal transition in detail.

    Q: How is endometriosis different from PCOS?
    A: Both conditions affect the reproductive system and can cause hormonal imbalance and fertility challenges, but they are distinct diseases with different causes and treatment approaches. PCOS (polycystic ovary syndrome) involves cysts on the ovaries related to hormonal imbalance and often elevated androgens, while endometriosis involves misplaced uterine-like tissue driven primarily by estrogen. A woman can have both conditions simultaneously, which is why thorough evaluation by a specialist is essential.


    Conclusion

    Endometriosis is a serious, complex condition — but it is far from a life sentence. With an accurate diagnosis, a personalized treatment plan, and a healthcare team that takes your symptoms seriously, most women with endometriosis are able to manage pain, protect their fertility, and live full, productive lives.

    The most important step you can take today is to stop minimizing your pain and start documenting it. Track your symptoms, ask questions, seek specialists when needed, and remember: pelvic pain that disrupts your life is never something you should simply push through.

    You deserve answers, and with the right support, you can get them. Always bring your concerns to a qualified healthcare provider who can evaluate your individual situation and guide you toward the most appropriate care.


    Medical Disclaimer: This article is for informational and educational purposes only. It does not constitute medical advice, diagnosis, or treatment. Always consult your physician or a qualified healthcare provider before making changes to your health routine or treatment plan.

    Medically reviewed by our editorial health team. Content follows evidence-based standards aligned with CDC and NIH guidelines.

  • PCOS: Symptoms, Causes & Treatment Options for Women

    PCOS: Symptoms, Causes & Treatment Options for Women

    Polycystic ovary syndrome affects millions of American women — yet nearly half go undiagnosed for years, silently struggling with symptoms they can’t explain.

    Introduction

    At 34, Jennifer had spent nearly a decade visiting doctors for irregular periods, stubborn weight gain, and facial hair that seemed to appear out of nowhere. Every time, she was told she just needed to "eat less and exercise more." It wasn’t until her third OB-GYN that someone finally connected the dots: she had polycystic ovary syndrome, or PCOS.

    According to the Office on Women’s Health, PCOS affects between 6% and 12% of US women of reproductive age — making it one of the most common hormonal disorders in the country. Yet despite its prevalence, the average woman waits nearly two years and sees multiple providers before receiving a correct diagnosis.

    If you’ve been dealing with irregular cycles, unexplained weight changes, skin issues, or difficulty conceiving, this guide is for you. We’ll walk through what PCOS actually is, what causes it, how it’s diagnosed, and what evidence-based treatment options look like in 2026 — so you can walk into your next doctor’s appointment feeling informed and empowered.

    What Is Polycystic Ovary Syndrome (PCOS)?

    PCOS is a hormonal and metabolic disorder in which the ovaries produce higher-than-normal levels of androgens — male hormones that women also have in smaller amounts. This hormonal imbalance disrupts the normal process of ovulation, often causing small fluid-filled sacs (follicles) to accumulate on the ovaries instead of releasing eggs as they should.

    Despite the name, not every woman with PCOS actually has cysts visible on an ultrasound, and not every woman with ovarian cysts has PCOS. The condition is defined by a cluster of findings, not by imaging alone.

    The CDC and NIH both recognize PCOS as a leading cause of female infertility in the United States. Beyond reproduction, PCOS carries significant metabolic implications: research published in the Journal of Clinical Endocrinology & Metabolism indicates that women with PCOS are at substantially higher risk for type 2 diabetes, cardiovascular disease, and endometrial cancer over their lifetimes.

    PCOS doesn’t go away after menopause. While ovulation-related symptoms may change, the metabolic and cardiovascular risks persist — making lifelong awareness and management critical for women’s long-term health.

    Signs and Symptoms of PCOS

    One reason PCOS is so frequently missed is that its symptoms vary widely from woman to woman. Some experience the full spectrum; others may have just one or two signs that seem unrelated on the surface.

    Early and Common Symptoms:

    • Irregular, infrequent, or absent menstrual periods
    • Heavy or prolonged menstrual bleeding when periods do occur
    • Excess facial or body hair (a condition called hirsutism)
    • Acne on the face, chest, or upper back that doesn’t respond to typical treatments
    • Thinning hair or hair loss on the scalp (similar to male-pattern baldness)
    • Difficulty losing weight or unexplained weight gain, especially around the abdomen
    • Darkening of the skin in creases — neck, groin, under breasts (called acanthosis nigricans)
    • Skin tags, particularly around the neck or armpits

    Signs Related to Fertility and Hormones:

    • Difficulty getting pregnant (anovulatory infertility)
    • Pelvic pain or pressure
    • Mood changes, depression, or anxiety
    • Sleep disturbances, including sleep apnea (more common in women with PCOS than the general female population)

    A 2022 meta-analysis published in Human Reproduction Update found that women with PCOS are nearly three times more likely to experience depression and anxiety compared to women without the condition — underscoring that PCOS is not just a reproductive issue but a whole-body health concern.

    This varies from person to person. Some women with PCOS have normal weight and relatively regular periods but struggle with androgen-related symptoms like acne and hair growth. Others have metabolic dysfunction as their primary concern. No two presentations are identical.

    Causes and Risk Factors

    The exact cause of PCOS isn’t fully understood, but research suggests it results from a combination of genetic, hormonal, and environmental factors working together.

    Hormonal Imbalances:
    Most women with PCOS have elevated levels of androgens (such as testosterone), which interfere with normal ovulation. Many also have higher levels of luteinizing hormone (LH) and lower levels of follicle-stimulating hormone (FSH), disrupting the cycle that triggers egg release.

    Insulin Resistance:
    Clinical evidence indicates that up to 70% of women with PCOS have insulin resistance — meaning their cells don’t respond effectively to insulin. This causes the body to produce even more insulin, which in turn stimulates the ovaries to produce more androgens, worsening the hormonal imbalance. The NIH notes that insulin resistance is a core driver of PCOS in many cases, not simply a side effect.

    Genetic Factors:
    If your mother or sister has PCOS, your risk is significantly higher. Research suggests a hereditary component, though the specific genes involved are still being studied.

    Low-Grade Inflammation:
    Studies have found that women with PCOS often have elevated inflammatory markers. This chronic, low-level inflammation may stimulate androgen production and worsen insulin resistance.

    Key Risk Factors Include:

    • Family history of PCOS, type 2 diabetes, or irregular periods
    • Obesity or excess weight, particularly abdominal fat
    • Sedentary lifestyle
    • Insulin resistance or prediabetes
    • Ethnic background — research suggests PCOS may be more common and more severe in Hispanic and South Asian women, though it affects women of all backgrounds

    It’s worth noting that PCOS occurs in women of all body sizes. Thin women can and do develop PCOS, though excess weight can amplify symptoms and worsen insulin resistance.

    Diagnosis: What to Expect

    There is no single test that definitively diagnoses PCOS. Instead, most physicians use the Rotterdam Criteria, which require that a patient meet at least two of three findings:

    1. Irregular or absent ovulation (reflected in irregular periods)
    2. Clinical or laboratory evidence of elevated androgens (excess hair, acne, or high testosterone on blood tests)
    3. Polycystic-appearing ovaries on ultrasound

    Your doctor will also want to rule out other conditions that can mimic PCOS, including thyroid disorders, elevated prolactin levels, and congenital adrenal hyperplasia — all of which require different treatment approaches.

    Tests you may undergo include:

    • Blood tests: total and free testosterone, DHEA-S, LH, FSH, estradiol, prolactin, TSH, fasting glucose, and insulin levels
    • A complete metabolic panel and lipid panel to assess cardiovascular and metabolic risk
    • Pelvic ultrasound to examine ovarian appearance
    • A1C test to screen for prediabetes or diabetes

    According to Mayo Clinic, PCOS is often first detected during a routine pelvic exam or when a woman seeks help for irregular periods or fertility concerns. The American College of Obstetricians and Gynecologists (ACOG) recommends that any woman with persistent irregular periods, signs of androgen excess, or difficulty conceiving be evaluated for PCOS.

    If you suspect you may have PCOS, don’t wait for symptoms to worsen. Early diagnosis leads to earlier intervention and a meaningfully lower risk of long-term complications like diabetes and heart disease.

    Treatment Options for PCOS

    PCOS has no cure, but its symptoms and underlying metabolic dysfunction are highly manageable with the right combination of medical treatment and lifestyle changes. Most physicians recommend an individualized approach based on your specific symptoms, whether you’re trying to conceive, and your overall health profile.

    Hormonal Contraceptives:
    For women who aren’t trying to get pregnant, combination oral contraceptives (estrogen and progestin) are often the first-line treatment. They regulate menstrual cycles, reduce androgen levels, and help clear androgen-related acne and hair growth. Clinical evidence from the American Journal of Obstetrics and Gynecology supports their effectiveness in managing PCOS-related symptoms over the long term.

    Metformin:
    Originally developed for type 2 diabetes, metformin is widely used in PCOS management because it improves insulin sensitivity. Research suggests it can help restore more regular ovulation, lower androgen levels, support modest weight loss, and reduce the risk of developing type 2 diabetes. Most physicians prescribe it alongside lifestyle modifications rather than as a standalone treatment.

    Medications for Fertility:
    For women trying to conceive, ovulation-inducing medications such as letrozole (often preferred over clomiphene in current clinical practice) are commonly prescribed. According to a landmark NIH-sponsored trial, letrozole resulted in higher live-birth rates in women with PCOS compared to clomiphene. Your reproductive endocrinologist can guide you through fertility treatment options.

    Androgen-Blocking Medications:
    Drugs such as spironolactone may be prescribed to reduce unwanted hair growth and scalp hair loss by blocking androgen receptors. These are typically used in women who aren’t planning pregnancy, as they can affect fetal development.

    Lifestyle Modifications — A Powerful Complement:
    This is where the evidence is especially strong. A 2020 systematic review in Obesity Reviews found that even a 5–10% reduction in body weight in women with PCOS who have overweight or obesity can significantly improve menstrual regularity, ovulation rates, androgen levels, and insulin sensitivity — sometimes dramatically.

    Key lifestyle strategies supported by clinical evidence include:

    • Low-glycemic diet: Prioritizing whole grains, legumes, non-starchy vegetables, and lean proteins while limiting refined carbs and added sugar helps stabilize blood sugar and reduce insulin spikes.
    • Regular aerobic and resistance exercise: Both improve insulin sensitivity independently of weight loss. The American Heart Association recommends at least 150 minutes of moderate-intensity exercise per week.
    • Stress management: Chronic stress elevates cortisol, which can worsen insulin resistance and hormonal imbalance. Mind-body practices like yoga, meditation, or cognitive behavioral therapy have shown benefit in small but growing clinical trials.
    • Adequate sleep: Poor sleep worsens insulin resistance and inflammation. Women with PCOS have higher rates of sleep apnea, which should be screened and treated if present.

    If you’re interested in how specific nutrients support hormonal balance and metabolic health, our guides on magnesium benefits for sleep and stress and omega-3 fatty acids cover evidence-based supplementation strategies that may complement your PCOS management plan.

    Living With PCOS: Long-Term Management and Prevention of Complications

    Managing PCOS is a long-term commitment — but it’s also genuinely achievable. Women who actively manage their condition reduce their risk of serious complications significantly.

    Monitor your metabolic health regularly. Most physicians recommend annual fasting glucose, A1C, and lipid panel testing for women with PCOS. Catching prediabetes or high cholesterol early gives you the best window for intervention. The American Diabetes Association recommends that women with PCOS be screened for diabetes every three to five years, or more frequently if other risk factors are present.

    Protect your heart. Women with PCOS are at elevated risk for hypertension and cardiovascular disease, particularly after menopause. Working with your doctor to maintain healthy blood pressure, cholesterol levels, and body weight is a critical part of long-term PCOS management. Our article on perimenopause symptoms and management may be especially relevant as you approach midlife, since PCOS and perimenopause can interact in complex ways.

    Protect your uterine health. Infrequent periods mean less frequent shedding of the uterine lining (endometrium), which over time raises the risk of endometrial hyperplasia and endometrial cancer. Your gynecologist may recommend hormonal treatment to induce regular withdrawal bleeds even if you’re not experiencing bothersome menstrual symptoms.

    Seek mental health support. The psychological burden of PCOS — from body image concerns to fertility stress to the exhaustion of managing a chronic condition — is real and significant. Therapy, support groups, and community resources are not extras; they’re part of comprehensive care.

    When to Call Your Doctor — Emergency Signs

    While PCOS itself is not a medical emergency, certain signs warrant prompt medical attention.

    Contact your doctor soon if you experience:

    • Periods that have stopped entirely for more than three months (if you’re not pregnant)
    • Sudden, significant worsening of symptoms such as rapid hair growth or deepening voice (which could suggest a different hormonal condition)
    • Severe pelvic pain
    • Signs of high blood sugar: excessive thirst, frequent urination, blurred vision, or extreme fatigue
    • Mood symptoms severe enough to affect daily functioning or include thoughts of self-harm

    Seek emergency care immediately if you experience:

    • Chest pain, shortness of breath, or sudden severe headache (possible cardiovascular event)
    • Signs of ovarian torsion — sudden, severe one-sided pelvic pain with nausea and vomiting — which is a surgical emergency
    • Heavy, uncontrolled vaginal bleeding

    At your next routine visit, consider bringing a written list of your symptoms, including when they started, how they’ve changed, and how they’re affecting your quality of life. The more specific you can be, the easier it is for your provider to tailor your care.

    Frequently Asked Questions About PCOS

    Can women with PCOS get pregnant naturally?
    Yes — many women with PCOS conceive naturally, though it may take longer due to irregular ovulation. Lifestyle changes alone can restore ovulation in some women. For those who need additional support, fertility treatments have strong success rates. Consulting a reproductive endocrinologist early can help you understand your specific options.

    Does PCOS go away after menopause?
    Not entirely. While menstrual irregularities and some androgen-related symptoms may ease after menopause, the underlying metabolic risks — including higher rates of insulin resistance, diabetes, and cardiovascular disease — persist. Ongoing monitoring and healthy lifestyle habits remain important throughout a woman’s life.

    Is PCOS the same as having ovarian cysts?
    No. Ovarian cysts can occur for many reasons and are extremely common. PCOS refers to a specific hormonal syndrome defined by irregular ovulation, elevated androgens, and often (but not always) a polycystic appearance on ultrasound. You can have ovarian cysts without PCOS, and you can have PCOS without visible cysts.

    Can diet alone treat PCOS?
    Diet is one of the most powerful tools in PCOS management, but it’s rarely sufficient on its own for every patient. Research suggests a low-glycemic, anti-inflammatory dietary pattern can significantly improve insulin sensitivity, hormone levels, and menstrual regularity — particularly in women with excess weight. However, many women benefit from a combination of dietary changes, exercise, and medical treatment. Work with your doctor to find the right balance.

    Is PCOS related to other health conditions?
    Yes. PCOS is associated with significantly higher rates of type 2 diabetes, prediabetes, high blood pressure, high cholesterol, fatty liver disease, obstructive sleep apnea, endometrial cancer, anxiety, and depression. This is why PCOS is best managed as a systemic condition — not just a gynecological one — with a care team that may include your OB-GYN, primary care physician, endocrinologist, and mental health professional.

    Conclusion

    PCOS is one of the most common hormonal conditions affecting American women — and one of the most underdiagnosed. If you’ve been dismissing your irregular cycles, persistent acne, or unexplained weight struggles as separate, unrelated problems, it may be worth having an honest conversation with your doctor about PCOS.

    The good news is clear: with the right diagnosis and an individualized treatment plan, most women with PCOS can manage their symptoms effectively, protect their long-term metabolic and cardiovascular health, and — when desired — achieve healthy pregnancies. You don’t have to accept years of confusion and inadequate care as the norm.

    Knowledge is your first and most important tool. Take it to your next appointment, ask the right questions, and advocate for the care you deserve.


    Medical Disclaimer: This article is for informational and educational purposes only. It does not constitute medical advice, diagnosis, or treatment. Always consult your physician or a qualified healthcare provider before making changes to your health routine or treatment plan.

    Medically reviewed by our editorial health team. Content follows evidence-based standards aligned with CDC and NIH guidelines.
